

Tag: heart health

  • Are You Worried About Statin Side Effects? Why 47% of Patients Stop Their Medication

    Are You Worried About Statin Side Effects? Why 47% of Patients Stop Their Medication

    Have you been prescribed a medication, like a statin, and worried about side effects? Did you stop your medication? Or maybe you never even started it.

    Traditionally doctors have relied on a ‘trial and error’ approach to medication.

    The “Trial-and-Error” Gamble with Statin Prescriptions

    Over 5 million people in the UK are prescribed statin medication every year. But we know that approaching 50% of patients stop them in the first year, or never even get their tablets.

    Either experiencing side effects or worry about them are two of the biggest reasons for this. This is a big problem for your health. Cardiovascular disease is the leading cause of death, but a massive 80% of cardiovascular disease is preventable. Controlling lipids with medications like statins is a key weapon to prevent deaths from cardiovascular disease.

    What is Pharmacogenomics (PGx)? The End of “One-Size-Fits-All” Medicine

    Pharmacogenomics analyses your DNA, looking at specific genes which dictate how your body responds to medicines. We have excellent detailed data that can predict how your body will metabolise drugs. This impacts not just whether the drug is effective, but also the risk of nasty side effects.

    In the clinic we take a simple blood sample which is analysed in a specialist genetic laboratory in Germany. The result gives us a detailed profile of your pharmacogenomics.

    How a Simple Genetic Test Can Predict Your Body’s Response to Statins

    The SLCO1B1 gene in your DNA codes for making a protein that is vital in controlling the metabolism of statins by your liver. We all have slightly different copies of this gene, called polymorphisms.

    Up to 36% of people tested have a copy of SLCO1B1 with decreased function. This means that the body has trouble clearing statins from the bloodstream to be metabolised by the liver. This means levels of the statin drug can build up in the blood stream, and cause side effects such as muscle pain and inflammation.

    A Patient Story: Replacing Statin Fear with Confidence

    In the clinic we can check your pharmacogenomic profile before starting medication. This means we can then choose a statin or other cholesterol lowering medicine which is much safer for you. You will be less likely to experience side effects and the drug is also more likely to be effective.

    We had a patient recently who wanted to start a statin to reduce their long-term risk of heart disease, they had read a lot about people experiencing muscle pain. As a really fit and active person they didn’t want anything which would impact their busy lifestyle. Their pharmacogenomic profile showed they have decreased SLCO1B1 function and were at high risk of side effects with the most commonly prescribed statins, atorvastatin and simvastatin. We were able to choose a low dose of rosuvastatin for them, this is the most effective and safest choice for them.

    Take the Guesswork Out of Your Heart Health

    We are incredibly lucky to be alive in a time where medical advances give us the chance for preventative healthcare. This chance was denied to many generations before us.

    We know though that many patients worry about taking medications, especially about unwanted side effects. Pharmacogenomics is a key tool we can use make sure you get the right medication. We can go from ‘trial and error’ to a truly personalised cardiovascular disease prevention plan.

    Interested in finding out your pharmacogenomic profile and what real-life personalised medicine means? We’d love to help you, so book today or get in touch.

    British Society for Genetic Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in BBC, The Guardian, Women’s Health, The Times and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.


  • Blood Pressure Is the Most Important Number You’re Ignoring

    Blood Pressure Is the Most Important Number You’re Ignoring

    When people talk about longevity, they usually mention things like cold plunges, mushroom powders, or the latest supplement that “everyone in Silicon Valley is taking.” But if you ask most doctors,  the kind who deal with real patients, not just podcasts, the top of the list is something far less glamorous, blood pressure.

    Blood Pressure: The Silent Killer That’s Surprisingly Common

    High blood pressure, or hypertension, is often called the silent killer. And for good reason. It doesn’t usually cause symptoms. There’s no rash, no pain, no warning light. But over time, it quietly raises your risk of heart attacks, strokes, kidney disease and dementia.

    When it comes to blood pressure, there’s a simple rule worth remembering. It’s known as the “Rule of Halves”:

    • About half of all adults have high blood pressure.
    • Half of those are undiagnosed.
    • Half of those who are diagnosed aren’t treated.
    • And half of those treated aren’t treated properly.

    That’s a lot of people wandering around thinking they’re in good shape because they “feel fine.”

    But I Had My Blood Pressure Checked at My GP Surgery…

    Let’s talk about how blood pressure is usually measured. You sit in a clinic. You’ve walked fast to get there or worried about parking wardens, probably had a coffee beforehand. Someone wraps a cuff around your arm and tells you to relax.

    That one-off reading might be useful, but it’s also a bit like checking the weather by glancing out the window for five seconds. You’re not getting the full picture.

    Enter the Hilo Band

    The Hilo Band is a wearable device that takes a different approach. It uses photoplethysmography (PPG),  a light-based sensor on your wrist, to monitor the shape and flow of your pulse wave. It’s not just counting your pulse. It’s analysing how your blood pressure behaves throughout the day and night using Pulse Wave Analysis (PWA).


    Hilo gives you multiple readings over 24 hours, including while you sleep. And the band only records when you’re still, which improves accuracy. It’s like having a calm, unobtrusive nurse quietly checking your pressure in the background. And yes, it looks good too. Like a minimalist fitness tracker had a child with a hipster bracelet.

    Real Life Data, Not Waiting Room Guesswork

    This continuous monitoring means you get a clearer, more accurate view of your blood pressure patterns. As opposed to a single, possibly elevated reading in a GP’s office. It can help catch masked hypertension (normal readings in clinic but high at home) or white coat syndrome (high in clinic, normal elsewhere).

    That matters because earlier detection means earlier action, which can include everything from lifestyle tweaks to proper medication, guided by real-world data rather than guesswork.

    Blood Pressure and Longevity: The Real Biohack

    If you’re serious about healthspan (although I hate that word as it sounds like management consultant jargon!), not just how long you live, but how well, then keeping your blood pressure in check is arguably more effective than most so-called biohacks.

    You don’t need exotic pills or 18-step routines. You need good sleep, a Mediterranean-ish diet, regular movement… and control of your blood pressure.

    If you’re going to invest in a wearable, make it one that actually improves your health, not just a random, clinically meaningless “health score.”

    If you’re ready to try it, check them out here: Hilo Band

    Blood pressure control isn’t new or flashy. But it works. And with a tool like the Hilo Band, it’s easier than ever to track, understand and act on. Because knowing your numbers, in your real life, not just under fluorescent clinic lights, is one of the smartest longevity moves you can make. 

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.
  • Why ApoB Matters For Your Heart Health

    Why ApoB Matters For Your Heart Health

    If you care about your heart, then you’ve probably been told to keep an eye on your cholesterol. For decades, low-density lipoprotein cholesterol (LDL-C) has been the poster child for cardiovascular risk. The higher your LDL-C, the higher your risk of heart attack and stroke. So we measure it, we target it, and we try to lower it.

    However, it is little known that LDL-C is just a proxy. What actually damages arteries is not the cholesterol floating around your blood, but the particles that carry it. Each of those particles has, on it’s surface, a protein called apolipoprotein B (apoB). The more apoB particles you have, the more chances they have to burrow into your artery walls and trigger atherosclerosis.

    ApoB is, in effect, a headcount of all the atherogenic particles in your blood. For years, evidence has been mounting that it is a better marker of risk than LDL-C. In 2019, European guidelines even stated that apoB was more accurate, easier to measure, and more precise. And yet LDL-C still reigns supreme in clinical practice.

    Why isn’t ApoB used more in clinical practice?

    The reason Apob is not used more frequently in current clinical practice is partly inertia. It is also partly habit. And it is partly the argument that LDL-C and apoB are so highly correlated, it makes no practical difference. If you lower one, you lower the other. So many cardiologists and primary care doctors would argue, why bother changing the guidelines?

    A new UK Biobank study has put that argument to bed.

    What this new study found about ApoB

    Researchers followed nearly 300,000 healthy adults for 11 years. They looked at LDL-C, non-HDL cholesterol, triglycerides and apoB, and tracked how each one related to future heart attacks and strokes.

    Yes, LDL-C and apoB were highly correlated. But the correlation was not perfect. At any given LDL-C level, individual apoB levels varied widely. Two people could have the same LDL-C, but one might have far more apoB particles quietly driving up their cardiovascular risk.

    Across every LDL-C or non-HDL-C level, people with higher apoB levels had significantly more cardiovascular events. ApoB gave extra risk information that LDL-C or non-HDL-C simply missed.

    When the researchers ran adjusted statistical models, apoB consistently came out on top as the stronger predictor of risk. LDL-C added no meaningful information once apoB was taken into account.

    Triglycerides too? Same story. ApoB still won.

    Some guidelines only recommend testing apoB if your triglycerides are high. The idea is that apoB might only be useful in those cases, when cholesterol particles are small and harder to measure accurately using standard tests. But this study found no support for that.

    In fact, apoB was consistently useful regardless of triglyceride levels. Even when triglycerides were taken into account, apoB still gave meaningful extra information about risk. The reverse wasn’t true. Once you knew someone’s apoB, their triglyceride level didn’t add much.

    This suggests apoB is giving us more useful insight, across the board, not just in people with high triglycerides.

    Because in clinical practice, we are treating individual patients, not population averages. Knowing your apoB level helps tailor your treatment far more accurately. Without it, there is too much guesswork. Two patients with the same LDL-C could have very different numbers of atherogenic particles, and very different risk.

    We now have safe and powerful therapies, from statins to PCSK9 inhibitors. But they are costly and need to be used wisely. ApoB is the best tool we have to target those therapies to the right people.

    Why has ApoB not been widely adopted yet?

    One argument that is frequently given is cost. But measuring apoB is inexpensive. In the US, it would raise lipid testing costs by about 1 percent. And in reality, once apoB is used, there is little need to keep measuring LDL-C or non-HDL-C, so the total cost of care need not rise.

    Another barrier is familiarity. Doctors and labs are used to ordering LDL-C. Changing habits takes time. But with evidence like this, the argument for change is becoming hard to ignore.

    ApoB is the best available measure of atherosclerotic risk. LDL-C and non-HDL-C are imperfect stand-ins. If you want the most accurate picture of your cardiovascular risk, you should know your apoB.

    If you are already on treatment, it is the best way to know if your therapy is working. If you are not yet on treatment but considering it, it can help you and your doctor make a better-informed decision.

    If guidelines and clinical practice catch up to the evidence, we will prevent more heart attacks and strokes. And that, surely, is the whole point.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • High Blood Pressure: The Longer You Have It, The Worse It Gets

    High Blood Pressure: The Longer You Have It, The Worse It Gets

    Walk into any supermarket and try to avoid ultra-processed foods. It’s nearly impossible. Ready meals, packaged snacks, ‘healthy’ protein bars, and supermarket bread. They all fall into this category. Even some foods marketed as nutritious are ultra-processed, full of additives, preservatives, and ingredients that barely resemble anything found in nature.

    We’ve long suspected they’re bad for us. But a massive new study has put the nail in the coffin. The more ultra-processed food you eat, the worse your health outcomes. Heart disease, obesity, type 2 diabetes, depression, and even early death; the risks go up across the board.

    High blood pressure (hypertension) is often called the “silent killer.” But let’s be honest, it’s not that silent. Your doctor has probably mentioned it. Maybe you’ve been told to “keep an eye on it” or “try to reduce your salt intake.” The problem is that by the time hypertension gets serious, it’s been quietly causing damage for years.

    A major new study has confirmed what many of us suspected. The longer you have hypertension, the worse the outcomes. The study looked at over 27,000 people and found that the duration of high blood pressure, not just the level, plays a crucial role in stroke risk and how hard it becomes to control.

    So, if you’ve been thinking, “I’ll deal with it later,” this one’s for you.

    The Key Findings: More Time, More Risk

    The study found three big problems with having high blood pressure for longer:

    1. Your stroke risk goes up.
      • People with high blood pressure for less than 5 years had a 17% higher risk of stroke.
      • Between 6-20 years, the risk jumps to 48% higher.
      • Over 21 years and the risk skyrockets to 86% higher.
    2. The takeaway is that high blood pressure isn’t just about the number on a screen. The longer your body has been under pressure (literally), the more likely you are to suffer a stroke.
    3. It gets harder to control.
      • The longer you’ve had hypertension, the more medication you need to keep it in check.
      • People with high blood pressure for less than 5 years were on 1.7 different meds.
      • Those with 6-20 years were on 2.0 meds.
      • Those with 21+ years? They needed an average of 2.3 different medications just to manage their numbers.
    4. Translation: If you develop hypertension early and don’t take action, it’s a one-way street to more pills and more complications.
    5. Even with meds, your blood pressure stays higher.
      • Longer hypertension = higher blood pressure, even with treatment.
      • This means more strain on your heart, arteries, brain, and kidneys.

    What You Can Do Right Now

    You don’t need to wait for a GP to tell you your blood pressure is creeping up. Here’s what you can do today:

    1. Get it checked.
    2. Move your body.
    3. Eat real food.
      • Ditch ultra-processed foods (see our last blog).
      • More potassium-rich foods like leafy greens, bananas, and nuts.
      • Cut back on salt, but don’t obsess.
    4. Strength train.
    5. Sleep properly.
    6. Sort out stress.

    Final Thought: Prevention > Treatment

    High blood pressure isn’t something that “just happens” when you get older. It’s the result of decades of lifestyle and genetic factors adding up.

    The best time to take action is before blood pressure rises. The second best time is now. 

    The longer you wait, the harder it gets to manage. But the good news? Even small changes can make a huge difference.

    What Should You Do?

    You don’t need to live like a monk. But cutting back on UPFs is one of the best things you can do for your health. Here’s how:

    • Stick to real food: If it had a face, grew from the ground, or needed little intervention before reaching your plate, it’s a good choice.
    • Shop the perimeter of the supermarket: That’s where you’ll find meat, fish, eggs, fruit, veg, and dairy.
    • Check the ingredients list: If it reads like a chemistry experiment, think twice.
    • Cook more at home: It doesn’t have to be complicated. Simple meals with whole ingredients will always beat processed alternatives.
    • Follow the 80/20 rule: You don’t have to eliminate UPFs completely, but they should be an occasional treat rather than a daily staple.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Harnessing the Power of Youth: A Long-term Look at Physical Activity and Heart Health

    Harnessing the Power of Youth: A Long-term Look at Physical Activity and Heart Health

    Legend has it that Finn McCool is not dead at all. Or it may be that Fionn MacCumhaill, often anglicised to Finn McCool, died in old age in battle, or having hit his head on a rock. What isn’t in doubt is that he must have lived to an old age. What was his secret? Well, perhaps it was that he did so much exercise in his youth.

    Today, if you spend any time on social media, advice on exercise seems to be extraordinarily complex. Yet one golden seam in the tapestry of health advice seems to stretch further and stronger with each passing study. That is the undeniable link between physical activity and heart health. The American Heart Association has long championed the mantra of achieving at least 150 minutes of moderate-to-vigorous physical activity (PA) per week as a beacon for cardiovascular disease prevention. But let’s face it, tracking our weekly quota of physical exertion can sometimes feel like taking a toddler to a Sunday pub lunch —unpredictable and overly optimistic.

    The Coronary Artery Risk Development in Young Adults study, decided to investigate how young adults’ dedication to physical activity (PA) could shape their cardiovascular destiny. This study sought to unearth the relationship between sustained physical activity in youth and the risk of heart-related events later in life. To do this it used a metric known as time in target range (TTR).

    The study corralled 2,902 participants into four groups based on their PA TTR. The underachievers (<25%), the middling masses (25% to <50%), the diligent doers (50% to <75%), and the overachievers (75% to 100%). TTR was calculated across a span of 15 years. This period was presumably filled with vigorous padel games and possibly ill-advised attempts at parkour.

    As the participants gracefully aged into their 40s, with a median follow-up period stretching nearly 19 years into the future, the fruits of their youthful exertions began to show. The overachievers, those with a TTR of at least 75%, flaunted a 40% lower risk of cardiovascular events compared to their less active counterparts. It seems that maintaining a high level of physical activity during those formative years could significantly shield one’s heart from future woes.

    But there’s a kicker. For every 1-SD increase in TTR, there was a 21% decreased risk of heart-related events. This suggests that even incremental improvements in sticking to exercise guidelines can pay dividends for future heart health.

    So, what’s the takeaway? Maintaining recommended levels of physical activity throughout young adulthood isn’t just a good idea. It’s a potentially life-altering strategy for warding off cardiovascular diseases later in life.

    Imagine if we treated our physical activity habits like a high-yield savings account for our health. The more we deposit in our youth, the richer we become in terms of vitality and longevity. This study underscores the importance of a life course approach to managing our heart health. It suggests that the seeds of cardiovascular well-being are sown early. These seeds need to be nurtured with the same zeal we apply to our careers, relationships, and Netflix binges.

    But what about those of us who may have missed the memo in our youth? It’s never too late to start. After all, in the journey of heart health, every step counts, no matter when you begin. Here’s to a heartier, healthier future, fueled by the enduring power of endurance exercise.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Tomatoes: A Natural Way To Improve Blood Pressure

    Tomatoes: A Natural Way To Improve Blood Pressure

    In the world of nutritional science, we often see people narrow focus to single nutrients. While I’m generally not a fan of this approach, a recent study on tomatoes and their potential to combat high blood pressure has caught my attention, and it’s really quite compelling.

    The PREDIMED Study: Tomatoes Blood Pressure Benefits

    The PREDIMED trial is an exploratory analysis involving 7,056 participants who have high blood pressure. It delivered some fascinating insights into the role of tomatoes in managing blood pressure. Who knew that these red fruits, often mistaken for vegetables, could improve cardiovascular health?

    Tomatoes vs. Hypertension: What the Data Says

    Participants in the study were grouped based on their tomato consumption, from the least (<44 g) to the highest (>110 g). Over three years, those with the highest intake showed a remarkable 36% reduction in the risk of developing hypertension compared to those who ate the least.

    The Science Behind the Scenes

    The secret sauce here seems to be lycopene, a potent antioxidant found abundantly in tomatoes. Around 85% of our lycopene intake comes from tomatoes and their derivatives. Lycopene is excellent at neutralising free radicals – those unstable molecules that cause cellular damage and contribute to various health issues, including hypertension.

    Lycopene’s Broader Impacts

    Beyond just mopping up free radicals, lycopene also plays a role in inhibiting the ACE enzyme, which is involved in blood pressure regulation. This dual action of lycopene not only helps in reducing hypertension but also has implications for broader cardiovascular health.

    Alternatives to Tomatoes for Lycopene Intake

    If you’re not a tomato fan, don’t worry. Lycopene is also found in pink grapefruits, pink guavas, watermelons, and papayas. Even processed tomato products like sauces and ketchups are rich in lycopene. The key is to find a balance that suits your palate and dietary preferences.

    The Takeaway: A Step Towards Better Health

    This study reiterates the age-old wisdom about eating fruits and vegetables, with a spotlight on tomatoes. Incorporating them into our diet, provides be a simple yet effective way to manage blood pressure and improve heart health.

    It’s important to remember that nutrition is more complex than single nutrients. But this study on tomatoes and lycopene presents an opportunity to make an impact reducing hypertension rates.

    So next time you’re contemplating your meal choices, remember that adding a splash of red might just be what your heart needs. 

    If you found this blog helpful we would love you to share it with your friends and family

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.
  • Lipid-Lowering Therapy in Older Adults: A New Danish Study Sheds Light

    Lipid-Lowering Therapy in Older Adults: A New Danish Study Sheds Light

    There’s been a longstanding debate about the effectiveness and necessity of lipid-lowering therapies, especially statins, in older adults. A recent Danish cohort study involving 65,190 individuals aged 50 and above has provided some illuminating insights into this topic. The rates of use of statin therapy has been shown to decline in people above age 75. This applies even to people who are known to have cardiovascular disease. The decline in statin usage is even more sharp in those who do not have cardiovascular disease.  

    The Conventional Wisdom and the Emerging Data

    Traditionally, the focus of lipid-lowering therapy, particularly aiming to reduce low-density lipoprotein cholesterol (LDL-C), has been on younger populations. But does this mean our approach should differ as we age? This study suggests perhaps not.

    What the Study Reveals

    The Danish research team embarked on an observational study using national healthcare and administrative registries to understand the impact of initiating lipid-lowering treatments in older adults. Their findings:

    * Substantial Risk Reductions: For each 1mmol/L reduction in LDL-C, there was a 23% decreased risk of major vascular events, regardless of whether individuals were older or younger than 70.

    * Uniform Benefits Across Ages: These benefits were consistent in both the older (≥70 years) and younger (<70 years) groups, indicating that age does not diminish the effectiveness of these therapies.

    * Supportive Observational Data: Complementing this data are findings from Giral and colleagues, who observed lower rates of cardiovascular events in those who continued statin treatment past the age of 75, compared to those who stopped. It included people who had taken statins regularly but hadn’t had heart problems before. The study found that stopping statins increased the risk of hospital admission for heart issues by 33%.

    Broader Implications and Future Directions

    This study aligns with data from the Cholesterol Treatment Trialists Collaboration and other primary prevention trials. The Cholesterol Treatment Trialists Collaboration has been running since 1994. It conducts meta-analyses of cholesterol intervention trials. The Collaborations aims to assess whether interventions on lipid-lowering work in different types of people. A meta-analysis allows a more reliable assessment of the effect of an intervention than a single trial alone. Previously, they have demonstrated that statin therapy does not increase the risk of cancer or of other non-cardiac causes of death. The key takeaway is that lowering LDL-C levels is crucial for reducing cardiovascular risk, regardless of age.

    Two prospective randomised trials are also on the horizon, promising to provide more clarity on this topic for older adults. These include the STAREE study, focusing on patients over 70, and the SITE/SAGA study, examining statin cessation in individuals 75 years or older. While we now have some clarity for over 50s, there is still debate as to whether statins are useful and cost-effective for over 75s. These two studies should provide some clarity.

    My Perspective

    The message here is clear: preventing cardiovascular events is a universal goal, transcending age barriers. These new findings reinforce the importance of managing cholesterol levels even in older adults. It’s not about the number of candles on a birthday cake; it’s about the numbers that count for heart health. 

    For our younger patients, it’s important not to delay statin treatment. A study in the journal  Circulation analysed data to uncover when younger adults should start statins to prevent heart disease over 30 years. It found that starting cholesterol-lowering treatments in your 40s, especially if your LDL is high, could significantly reduce the risk of heart disease later on. This study suggests it might be more important to decide when to start treatment rather than if you should start at all.

    Make sure you have your discussed your risk of cardiovascular disease and discussed a plan to lower your risk with your GP.

    Please help another person improve their heart health by sharing this blog.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.
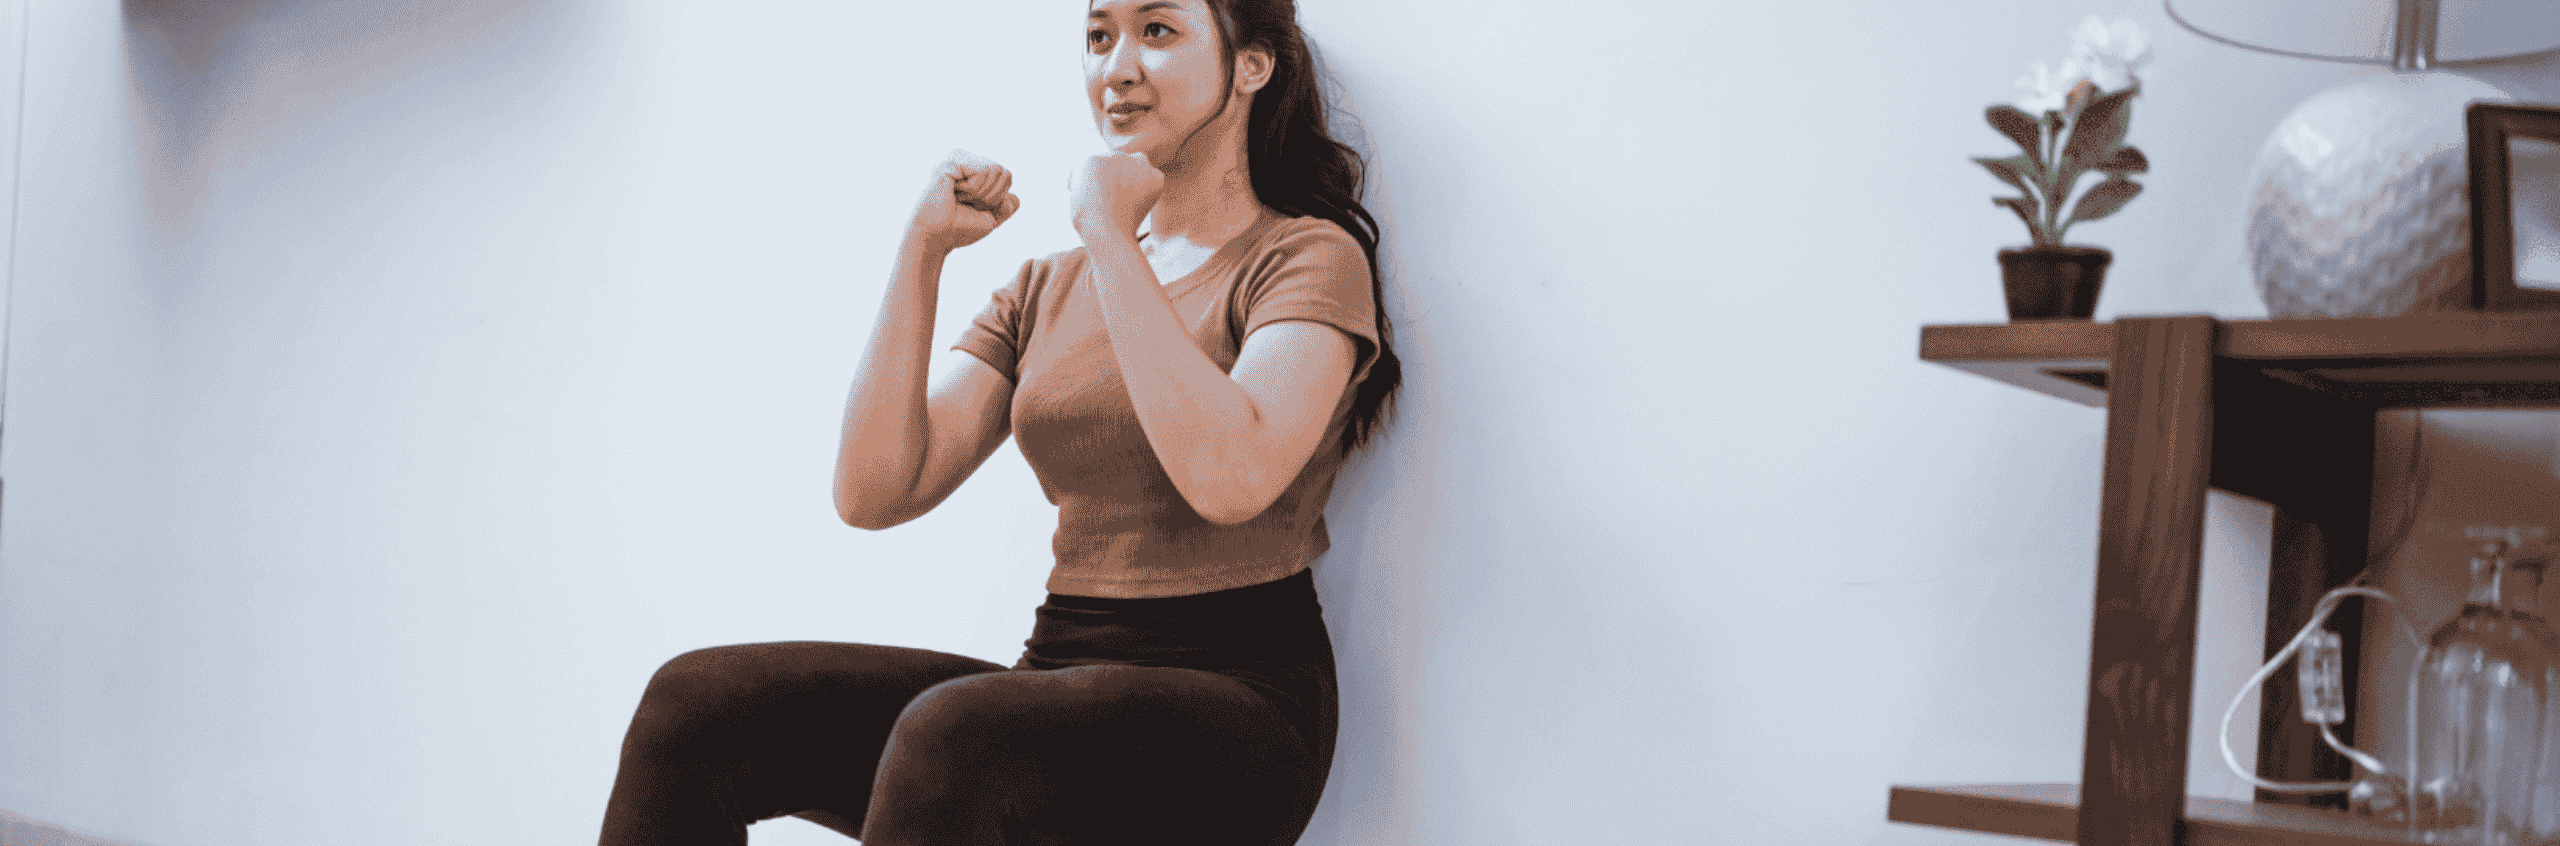
  • The Best Exercise For Managing High Blood Pressure

    The Best Exercise For Managing High Blood Pressure

    High blood pressure, or hypertension, remains a global health challenge, with a soaring prevalence (thanks in part to changing definitions of hypertension) and control often proving elusive. It remains one of the leading modifiable risk factors for disease and death worldwide. While lifestyle interventions have long been a mainstay in hypertension management, a growing body of research underscores the particularly pivotal role of exercise training as an effective non-pharmacological antihypertensive strategy. Recent findings, including a large-scale systematic review and meta-analysis of 270 randomised controlled trials, shed new light on the optimal exercise practices for managing blood pressure. 

    Exercise as a Cornerstone of Hypertension Management:

    The link between exercise and cardiovascular health is certainly not a novel concept. Regular physical activity has long been associated with reduced risks of heart disease and hypertension. However, contemporary research is refining our understanding of how different exercise modalities impact blood pressure.

    The Landmark Study:

    Led by Dr. Jamie J. Edwards and a team of researchers from Canterbury Christ Church University in the United Kingdom, this comprehensive study published in the BJSM examined the effects of various exercise training modes on resting blood pressure. The study analysed 270 randomised controlled trials published between 1990 and February 2023, involving a total of 15,827 participants.

    Key Findings:

    The study’s results paint a clear picture of the effectiveness of different exercise modalities in reducing both systolic and diastolic blood pressure:

    • Aerobic Exercise Training: This traditional form of exercise demonstrated significant reductions in resting systolic blood pressure (SBP) by an average of 4.49 mm Hg and diastolic blood pressure (DBP) by 2.53 mm Hg.
    • Dynamic Resistance Training: Participants engaging in dynamic resistance training experienced reductions in SBP and DBP by an average of 4.55 mm Hg and 3.04 mm Hg, respectively.
    • Combined Training: Combining aerobic and resistance training led to even more pronounced reductions, with SBP decreasing by 6.04 mm Hg and DBP by 2.54 mm Hg.
    • High-Intensity Interval Training (HIIT): HIIT, known for its time-efficient, intense bursts of activity, lowered SBP by 4.08 mm Hg and DBP by 2.50 mm Hg.
    • Isometric Exercise Training (IET): This novel form of exercise emerged as the most effective, resulting in a substantial reduction of SBP by 8.24 mm Hg and DBP by 4.00 mm Hg.

    Optimal Exercise Modes:

    The study ranked the exercise modalities based on their effectiveness, with isometric exercise training (IET) topping the list, boasting a Surface Under the Cumulative Ranking Curve (SUCRA) value of 98.3 percent. Surface Under the Cumulative Ranking Curve, or SUCRA, is a statistical tool used in network meta-analysis to evaluate the relative effectiveness of several different interventions or treatments. In the context of this study, SUCRA values were used to assess and rank the various exercise modalities in terms of their impact on resting blood pressure.

    A higher SUCRA value indicates a greater likelihood that a particular intervention (in this case, an exercise modality) is the most effective among the options being compared. In other words, a higher SUCRA value suggests that an exercise mode is more consistently and confidently ranked as the best choice for reducing blood pressure. Combined training followed closely at 75.7 percent, dynamic resistance training at 46.1 percent, aerobic exercise training at 40.5 percent, and high-intensity interval training (HIIT) at 39.4 percent.

    The Isometric Advantage:

    Isometric exercise training, particularly through activities like isometric wall squats, emerged as the most potent submodes for reducing SBP (SUCRA: 90.4 percent) and DBP (SUCRA: 91.3 percent), respectively.

    Implementing Isometric Training:

    Isometric exercise places the muscle under tension without moving the surrounding joints. To harness the benefits of isometric exercise, use the following protocol:  

    4×2-minute contractions, separated by 1–4-minute rest intervals, performed three times a week. 

    Isometric handgrip (IHG) is usually executed at 30% maximum voluntary contraction, while isometric wall squats (IWS), also known as ski squats can be performed to elicit a rate of perceived exertion (RPE) between 3.5–4.5/10 for the first bout, RPE 5–6/10 for the second bout, RPE 6.5–7.5/10 for the third bout, and RPE 8–9/10 for the fourth bout. Isometric leg extension (ILE) is performed at 20% of the maximum voluntary contraction (this is the maximum amount of force that can be generated by contracting a muscle group). So in practice, this means holding still with the legs fully straightened approximately 20% of the heaviest hold that you could shift on the leg extension machine. 

    As the prevalence of hypertension continues to rise, understanding the role of exercise in its management becomes increasingly critical. The latest research emphasises the varied and substantial benefits of lots of different exercise modalities, with isometric exercise training shining as a particularly potent antihypertensive intervention. Of the isometric exercises, wall squats, to me at least, are the most convenient to perform.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Menstrual Cycle and Cardiovascular Health: A New Perspective for Women

    Menstrual Cycle and Cardiovascular Health: A New Perspective for Women

    Cardiovascular disease (CVD) remains the leading cause of death and disease for women worldwide. In Western countries, approximately 45% of women aged over 20 years are affected by CVD, and it accounts for one-third of all female deaths. Recognising the unique sex-specific aspects in preventing CVD is crucial as historically, studies in cardiovascular disease have frequently focused on men. Recently, there has been growing interest in studying menstrual cycle characteristics and their potential impact on cardiovascular health. 

    Regular menstrual cycles are a vital sign of women’s overall health, signalling normal functioning of the hypothalamic-pituitary-ovarian axis. However, about 20% of women of reproductive age experience irregular and long menstrual cycles due to endocrine disorders that disrupt this axis. These menstrual irregularities have been linked to several health conditions, including insulin resistance, metabolic disturbances, hyperandrogenism, and chronic inflammation. Consequently, they have been associated with an increased risk of coronary heart disease and related mortality, obesity, and type 2 diabetes.

    To gain further insights into the connection between menstrual cycles and CVD, researchers conducted a large population-based cohort study using data from the UK Biobank. This study included over 58,000 women aged 40 to 69 years who had no pre-existing cardiovascular disease at the study’s outset. Participants were asked to report their current menstrual cycle length and regularity. The researchers followed these women for a median duration of 11.8 years, tracking the development of incident CVD cases through national health records and follow-up visits.

    The study revealed some compelling associations between menstrual cycle characteristics and cardiovascular health. Here are the key findings:

    • Women with irregular menstrual cycles were found to have a 19% higher risk of CVD events, including heart disease and atrial fibrillation, compared to those with regular menstrual cycles.
    • Short (≤21 days) menstrual cycles were associated with a 29% higher risk of CVD events, while long (≥35 days) menstrual cycles showed an 11% increased risk. Specifically, short cycles were linked to a greater risk of coronary heart disease and myocardial infarction.
    • Both short and long menstrual cycles were associated with a higher risk of atrial fibrillation.
    • Interestingly, there was a significant interaction between irregular menstrual cycles and lower high-density lipoprotein cholesterol levels and smoking status, suggesting that these factors might influence CVD risk.

    This study adds to the growing body of evidence suggesting that menstrual cycle characteristics throughout a woman’s reproductive lifespan could be associated with cardiovascular disease. Although the findings are significant, more research is needed to fully understand the underlying mechanisms and establish causality. Future studies are crucial to fill the remaining knowledge gaps and determine on how menstrual cycles might be prospectively linked to cardiovascular disease and subsequent events.

    As we strive to ensure that women’s heart health is finally given the prominent status it deserves, understanding the potential impact of menstrual cycle characteristics on cardiovascular health becomes increasingly vital. The findings from the UK Biobank study provide valuable insights into the associations between irregular, short, and long menstrual cycles and CVD risk in women. Armed with this knowledge, women can take proactive steps towards better cardiovascular health. Regular check-ups, maintaining a healthy lifestyle, and discussing any menstrual irregularities with healthcare professionals can go a long way in safeguarding against CVD. 

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Unmasking the Hidden Enemy: Inflammation’s role in Cardiovascular Disease

    Unmasking the Hidden Enemy: Inflammation’s role in Cardiovascular Disease

    Cardiovascular diseases (CVDs) have long been a significant health concern, but advancements in statin therapy have helped reduce their impact. However, some patients continue to experience CVD events despite high-dose statin treatment. This is known as residual risk. Recent research suggests that this residual risk may be attributed, in part, to inflammation, which can trigger plaque ruptures. Here, we will delve into inflammation’s role in cardiovascular disease and explore the potential benefits of reducing inflammation using low-dose colchicine.

    Inflammation’s role in Cardiovascular Disease

    Inflammation has emerged as a key player in the development and progression of cardiovascular disease. Dr. Ridker and his team pioneered the use of high-sensitivity C-reactive protein (hs-CRP) testing to identify inflammation in patients. Their study, the Jupiter study, demonstrated the efficacy of rosuvastatin in reducing CV events in high-risk primary prevention patients identified through hs-CRP testing. However, the full potential of the inflammation strategy was not realised at that time and the potential to treat lower-risk patients was missed.

    Uncovering the Link between Inflammation and CV Events

    recent paper explored the connection between inflammation and CV events by analysing data from three major studies: PROMINENT, REDUCE-IT, and STRENGTH. Patients were divided into quartiles based on their hs-CRP levels, and the highest quartile group was compared to the lowest.

    The results were striking. Patients in the highest hs-CRP quartile experienced a 31% increase in major adverse cardiovascular events (MACE), a 268% increase in cardiovascular mortality, and a 242% increase in all-cause mortality, highlighting the significant impact of inflammation on CV health. Comparatively, the differences in MACE, CV death, and all-cause death were not as pronounced when comparing the highest and lowest LDL-cholesterol (LDL-C) quartiles. 

    The Inflammation Conundrum

    Once patients are on effective statin therapies and their LDL-C levels are well-controlled, the threat posed by LDL-C diminishes. However, the presence of inflammation remains a driving force behind future CV events. Identifying patients with high hs-CRP levels while on high-dose statins becomes essential to intensify efforts in reducing their residual CV risk.

    Addressing Inflammation: A New Frontier in Cardiovascular Health:

    Presently, there are limited affordable therapies proven to reduce inflammation. As a result, it is crucial to prioritise preventive measures that can help combat inflammation and its consequences. Encouraging patients to quit smoking, manage abdominal obesity, reduce stress, improve sleep quality, and adopt a heart-healthy diet can significantly contribute to reducing inflammation and enhancing overall cardiovascular health. 

    The Concern of Inflammation Post COVID-19

    The aftermath of long COVID poses another concern, as inflammation from COVID-19 may also increase the risk of cardiovascular events in a large number of people. Vigilance and proactive management of inflammation in recovering COVID-19 patients are paramount to safeguard their heart health.

    The Power of Low-Dose Colchicine

    Colchicine has been used for centuries to treat joint inflammation and is frequently used to treat gout.  A recent analysis has shed light on the potential of low-dose colchicine, revealing its significant impact in the management of chronic coronary artery disease by reducing inflammation in the coronary arteries. 

    The study conducted an in-depth analysis to model the 10-year and lifetime impact of low-dose colchicine in patients with chronic coronary artery disease. The results were striking, demonstrating that low-dose colchicine has the potential to bring about a median 10-year absolute risk reduction rate of 4.6% for major adverse cardiovascular events (MACE). This reduction in risk translates into gaining 2.0 MACE-free years over a lifetime for patients.

    What makes this finding even more significant is that the estimated 10-year and lifetime benefits of low-dose colchicine are comparable to the benefits associated with intensified low-density lipoprotein cholesterol (LDL-C) and systolic blood pressure-lowering. LDL-C and blood pressure optimisation are well-established strategies in cardiovascular management, and the fact that low-dose colchicine holds similar potential is indeed promising news.

    An exciting opportunity for patients with existing chronic coronary artery disease

    The discovery of the potential benefits of low-dose colchicine presents an exciting opportunity for patients with existing chronic coronary artery disease. By adding this medication to their treatment regimen, they may experience substantial improvements in their cardiovascular health, with a reduced risk of MACE over the long term.

    Low-dose colchicine is well-tolerated and has been used for years to treat conditions like gout. As always, individual patient needs vary, and decisions about treatment should be made in consultation with healthcare providers. When managing chronic coronary artery disease, healthcare providers will consider various factors, including a patient’s medical history, risk profile, and other existing treatments. By adopting a personalised approach to care, patients can receive the most suitable treatment plan that aligns with their unique health requirements.

    Hope for a healthier & heart-protected future

    Inflammation has emerged as a critical factor in the pathogenesis of cardiovascular disease, even when LDL-C levels are well-controlled through statin therapy. Identifying patients with inflammation through hs-CRP testing can help us address their residual CV risk and implement personalised strategies to reduce inflammation. The analysis of low-dose colchicine’s impact on chronic coronary artery disease has revealed its potential to significantly reduce the risk of major adverse cardiovascular events by reducing coronary artery inflammation. The estimated 10-year and lifetime benefits are on par with those of established cardiovascular therapies like LDL-C and blood pressure optimisation. Low-dose colchicine offers an exciting new option for enhancing cardiovascular health, providing patients with hope for a healthier and heart-protected future.

    If you have chronic coronary artery disease

    If you have chronic coronary artery disease, consider discussing the potential benefits of low-dose colchicine with your healthcare provider. Together, you can create a tailored treatment plan that best suits your needs, helping you embark on a journey towards improved cardiovascular well-being. Remember, your heart health is paramount, and with the right care and support, you can take positive steps to protect your heart and live a fulfilling life.

    Please reach out to the team if you have any questions about the contents of this article.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.