
Tag: heart health

  • Why Heart Disease Is Like Street Crime – CT Coronary Calcium Scores

    Why Heart Disease Is Like Street Crime – CT Coronary Calcium Scores

    Why Heart Disease Is Like Street Crime

    Broken windows theory was proposed in 1982 by Political Scientist James Quinn Wilson and Criminologist Geroge Kelling. The idea was that small crimes and misdemeanours inevitably led to serious crimes. This idea was taken on by New York Police Commissioner William Bratton. He cracked down on petty crimes and as a result, serious crime in New York fell. 

    Some people have a lipid profile that puts them at increased risk of cardiovascular disease. If you have a high Apolipoprotein-B (Apo-B) and high LDL particle number (LDL-p), for example, you are at higher risk of cardiovascular disease. This is because a high LDL particle number means that LDL is likely to break into the wall of the artery, cause inflammation and lead to coronary heart disease. It gets into the wall of the artery thanks to Apo-B. Having high Apo-B and LDL-p is analogous to living in a bad neighbourhood. If you have high Apo-B and LDL you are likely to have a break-in (to the arterial wall). Coronary calcium is a sign that damage has occurred in the arterial wall and reflects the body’s healing in response to damage. It is like having a boarded-up window after it has been smashed by a hooligan in a bad neighbourhood. We know from commissioner Bratton that broken windows inevitably lead to serious crime. In much the same way, coronary calcium is a signal that something serious is going to happen in the arterial wall. 

    Coronary artery calcium scoring (CACS) examines calcium deposits in the coronary arteries that occur during atherosclerotic plaque formation. The study takes around 10 minutes, doesn’t use contrast and the radiation dose is low (approximately 1 mSv). This amount of radiation is comparable to around two screening mammograms. The average person is exposed to approximately 2.7mSv radiation per year in the UK according to Public Health England. 

    Calcification in the arteries is due to the repair of the damage caused by the formation of atherosclerotic plaque. CACS provides an overall assessment of the amount of calcification, most commonly using the Agatston Score. As an interesting aside, Arthur Agatston not only developed the scoring system for measuring coronary artery calcium but also the South Beach Diet. 

    The initial evidence of the value of coronary calcium was provided by the landmark Multiethnic Study of Atherosclerosis (MESA). This was a study of 6814 individuals from four major ethnic groups. The study found a strong association between calcium score and adverse coronary events over almost 4 years of follow-up.  Subsequent studies have shown the benefit of calcium scoring in a variety of ages, sexes and clinical risk factor burdens.

    The addition of calcium scoring to our traditional risk estimation improves our identification of a patients chance of cardiovascular disease. It is particularly useful who allowing us to better understand who would and would not benefit from having medications to prevent cardiovascular disease such as statins or aspirin.

    A key advantage of calcium scoring is that while high scores are associated with elevated cardiovascular risk, the absence of coronary calcium is a negative risk marker that confers a good prognosis. This is what is known as negative predictive value. The negative predictive value of zero coronary calcium appears to be greatest in individuals at intermediate risk by traditional risk calculators. 45% of these patients will have CAC = 0, placing them at low cardiovascular risk and removing the need for preventive therapy such as statins. Conversely, the power of zero coronary calcium is limited in individuals who are already at high risk. Nearly 50% of fatal MIs occur in non-calcified areas of coronary arteries.  So even if the calcium score is zero, the patient may still need aggressive intervention if they live in a ‘bad neighbourhood.’ That is, even if they have a normal CAC but have very high ApoB and LDL-p. This is because they may have soft plaque and CAC does not show soft plaque.  

    European Society of Cardiology guidance on CVD preventiondyslipidaemia, and chronic coronary syndrome have all recognised the important role of CACS in the CVD risk assessment on an individual patient screening basis. They advised that CACS may improve risk classification in patients without symptoms in the moderate or low-risk categories. At levels of risk above this, significant lifestyle changes and potential medications are indicated. 

    So, CACS, seeing the amount of boarded-up windows in your neighbourhood, can considerably improve our estimation of your risk of cardiovascular disease and can be extremely helpful in guiding decisions on preventative treatment. 

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Going Beyond ‘Cholesterol’

    Going Beyond ‘Cholesterol’

    When most people have their cholesterol level checked they will usually have their ‘total cholesterol,’ LDL-C (the concentration of LDL), HDL-C (the concentration of HDL), triglycerides (TG), and non-HDL measured. However, while these measurements are of some use in estimating the risk of cardiovascular disease they do not give the full picture. More important than the mass concentration of the cholesterol-containing particles is the number of cholesterol particles and more besides. 

    When most people think about cholesterol they think that there is a good type and a bad type. In fact, all cholesterol is good. Cholesterol is vital to our existence. It is one of the most important constituents of our cell membranes. Not only do cell membranes provide structural support for the cell but they also facilitate how cells move, what goes in and out of cells and how cells interact with each other. Cholesterol is also essential in the production of steroid hormones, vitamins and bile acids which help digestion. 

    So cholesterol is good. It is only bad when it is in the wrong place and the wrong place for cholesterol to be is in the arterial wall. But how does cholesterol get there. 

    Only about a quarter of the cholesterol in our bodies comes from what we eat. The rest is produced by our bodies. Our liver manufactures about a fifth of the cholesterol made by our bodies. Of the cholesterol that we eat, most of it is not absorbed by our gut. So the amount of cholesterol that we eat only has a limited effect on the cholesterol levels in the body. 

    I think of the process of coronary artery disease as being a bit like my stag do in Bratislava. This may seem like a stretch, but bear with me. Think of the guys on the stag do as being like cholesterol particles. Just like the members of a drunken stag do in an unfamiliar town, cholesterol needs something to take it around the body. The things that help transport cholesterol around the body are called apoproteins. These are like the group of girls from a tour operator that the best man hires to take the stag do on a tour of the town’s bars. In the bloodstream, the cholesterol particles and apoproteins when packaged together are called apolipoproteins. These cholesterol particles with their apoprotein chaperones (aka apolipoproteins) all bundle together. The group of cholesterol particles and its apoprotein chaperone is called a lipoprotein.

    Just like the group of girls from a stag-do tour operator, apoproteins help keep the group together and facilitate communication between the group and those outside the group. Apoproteins also help act as cofactors in enzyme reactions. This is akin to the female tour guides getting the stag group a round of free drinks when they arrive in a bar.  

    There are two important types of apolipoprotein – A and B. Apolipoprotein B (apoB) is almost always found with low-density lipoprotein (LDL). Think of low-density lipoprotein as a stag do with a female tour guide. Apolipoprotein A (apoA) is almost always found with high-density lipoprotein (HDL). Think of HDL as a tour group from a cruise ship with a nice tour guide. The are not going to cause trouble (unless the town is totally overrun with cruise ships and tour groups). An important point here, there is one ApoB molecule with one LDL particle. Each LDL particle is actually a group of cholesterol particles.  

    Most stag dos attract a few hangers-on. In the body, these unhelpful hangers-on are triglycerides. As the lipoproteins transport the cholesterol around the body these hangers-on drop away. Much the same happens on a stag do as it progresses.  

    The lining of an artery is called the epithelium. To cause atherosclerosis, i.e. cardiovascular disease, the LDL particle has to enter the endothelium. If you can imagine the lining of the artery as being like a strip of nightclubs and bars and the lumen of the artery as being like a road. The stag do, of course, are the LDL particles. Apoprotein B can get the stag do into the cool club. Each stag do needs to have a girl with them to get in (because there is there is one ApoB molecule with one LDL particle). In the same way, to get into the lining of the arterial wall, each LDL particle needs an Apolipoprotein B to chaperone past the bouncer on the door. In case you’re wondering, the bouncer in this instance is called NPC1L1Niemann-Pick C1-Like 1 or NPC1L1 for short. 

    So what is it that causes LDL to go into the lining of the artery? Remember, conventional blood tests for cholesterol measure the concentration of the different lipoprotein subfractions. But, it is the number of particles of LDL that is more important. Think of it this way. The more small stag do groups there are the easier it is for each stag do to get into a bar. No bouncer is going to let a massive number of drunk guys in one big group into a bar. Bigger stag dos with more people in each of them are less likely to get into a bar. In the same way the higher the number of LDL particles the greater the chance they have of getting into the wall of the artery. Although LDL concentration may correspond to particle number, often it doesn’t. 

    Indeed, it has been found that the best predictor of the risk of cardiovascular disease is LDL particle number. Furthermore, those people at the highest risk had a low (normal) LDL-C and a high LDL particle number. In medical statistics, when two variables that usually track together do not track together, it is known as discordance. People who have high LDL-C and high LDL particle number are also at high risk but not as high as those with discordant values. Thinking about it in stag-do terms, the highest risk of trouble comes when lots of small stag dos are let into a bar. In the opposite scenario if there is just one stag do allowed in but it is large with lots of people who know each other the chance of trouble is low. That is, if there is a high LDL-C and low LDL particle number the risk of cardiovascular disease is actually less. As I have mentioned, having a large number of LDL particles and a high LDL-C is also a high risk for cardiovascular disease. It’s just not as high risk as having low LDL-C and high particle numbers. Even in patients who show up to the hospital having a heart attack, frequently their LDL-C is normal.

    People with metabolic syndrome are more likely to have an unhelpful discordant relationship between LDL-C and LDL particle number. Metabolic syndrome is a condition in which people have raised triglycerides (a storage fat in the blood), raised blood pressure, elevated waist circumference and elevated blood sugar. 

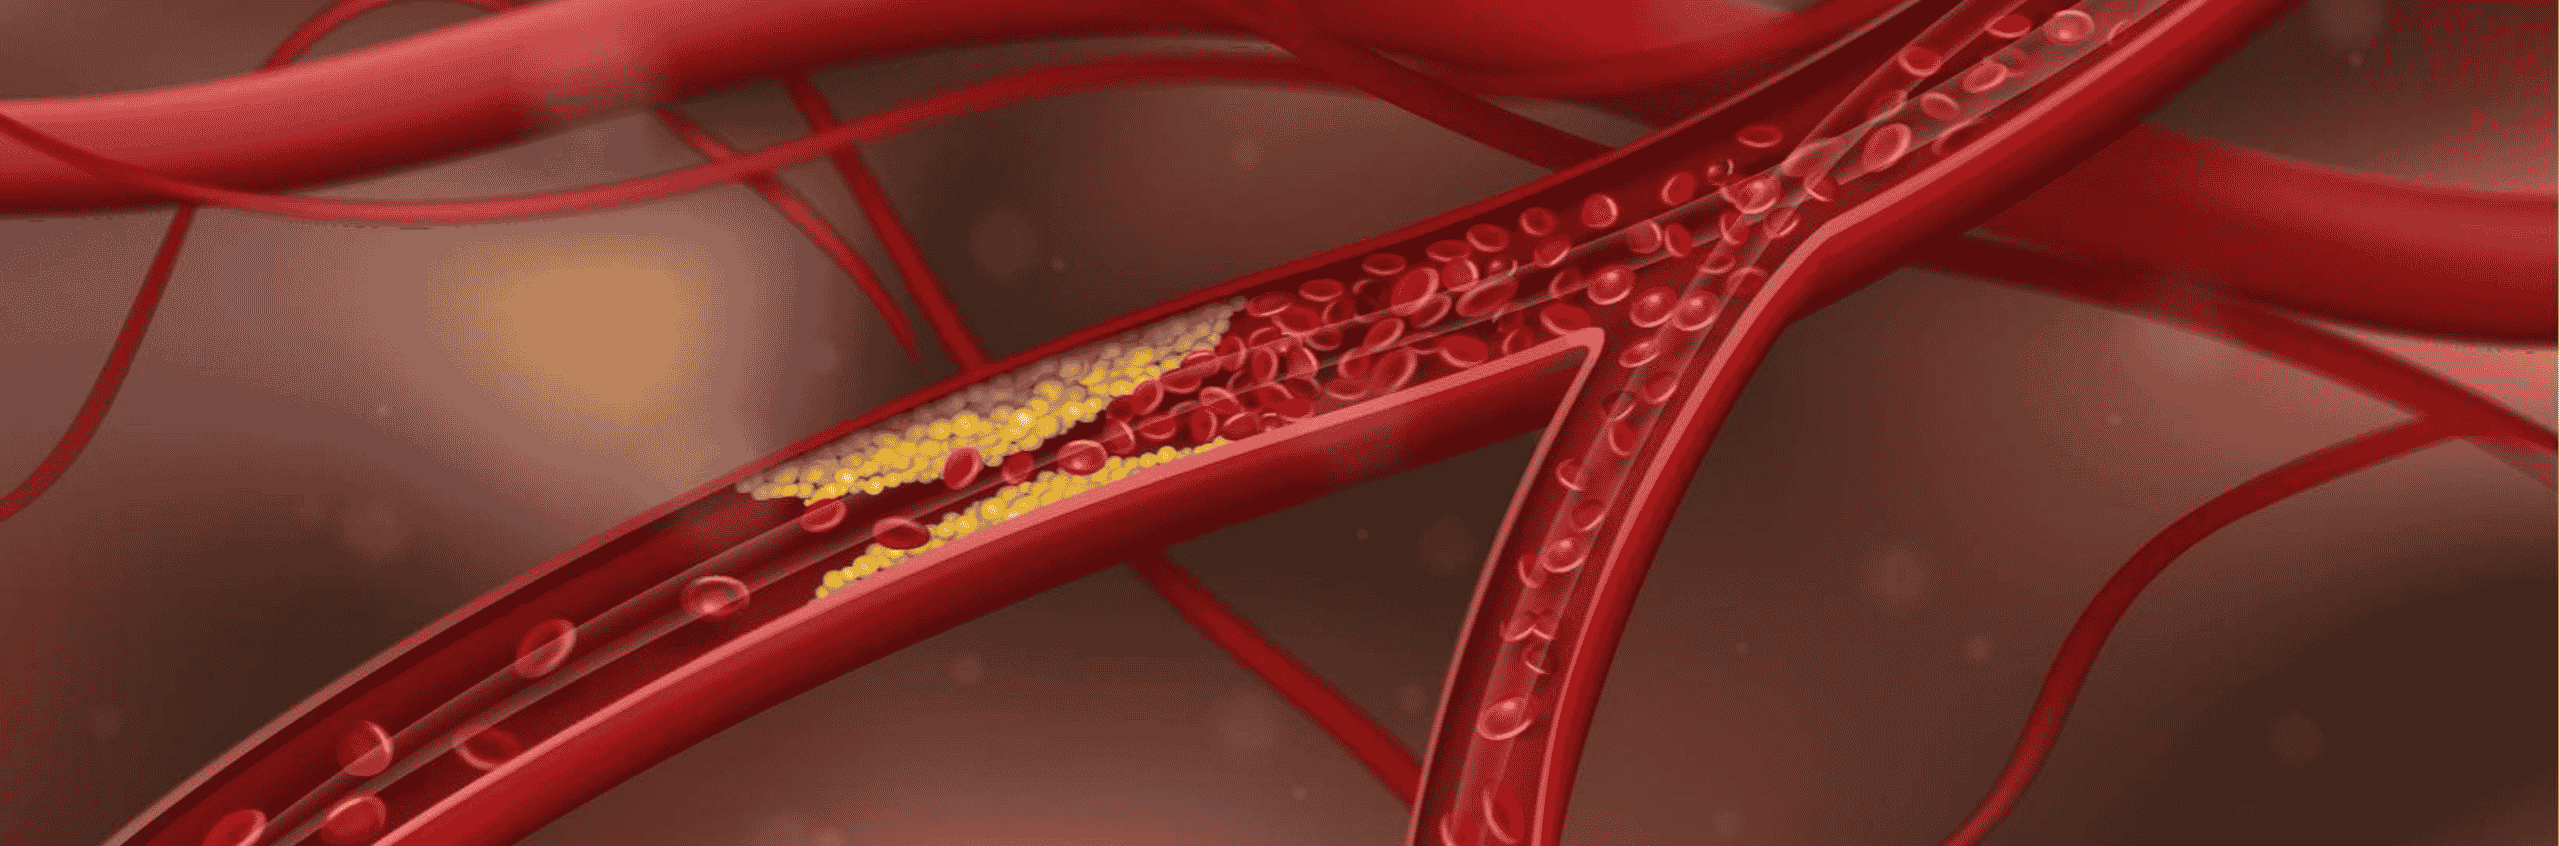
    Once inside the club (the arterial lining) the stag do (LDL) causes all sorts of problems. Imagine members of the stag do hitting on local girls, being generally obnoxious and riling up groups of local guys. The same happens when LDL enters the endothelium – absolute pandemonium. This leads to inflammation in the arterial wall. On a stag do, the groups of locals might try to get rid of the stag do. But there are too many guys on the stag do. As you can imagine, the bar gets damaged. A brawl ensues and it spills out onto the street. Pretty much the same happens to the endothelium of the artery. The inflammatory response causes an arterial plaque to form which spills over into the lumen eventually causing a clot to form, blocking the artery. Think of the clot as the police being called. They then block off the street. This obviously means that bars and clubs further down the street have to close. This is equivalent to tissue ischaemia in our bodies where a lack of blood supply causes the tissues downstream to die. This is the process of a heart attack.  

    So although LDL-C can give us some information on the likelihood of having a heart attack, it is nowhere near as good as knowing the LDL particle number. Measuring this requires nuclear magnetic resonance spectrometry. This is very expensive. As there is one LDL per ApoB it turns out that ApoB is a good proxy for estimating LDL particle number and therefore cardiovascular risk. Indeed, several studies, including AMORIS, INTERHEART, IDEAL and the Leiden Heart Study have demonstrated that ApoB is superior in predicting cardiovascular disease risk. ApoB level is also useful in finding out how effective lifestyle changes and treatments have been. According to the INTERHEART and AMORIS trials, the best risk predictor of cardiovascular disease is the ratio between ApoB and ApoA1.  

    Ischaemic heart disease is, to a great extent, inflammatory. The real problem is not so much the presence of the LDL particle in the artery wall. It is the inflammatory response to the LDL that is the problem. LP-PLA is a marker of arterial inflammation and suggests that the formation of unstable plaques in the arteries is occurring. In our stag-do analogy, Lp-PLA is the equivalent of a group of bouncers entering the melee. It suggests that the arteries are angry and that arterial plaque is forming. The PLAC test measures the amount of lipoprotein-associated phospholipase (Lp-PLA2) in the blood. Lp-PLA is a key player in making plaques that line the arterial wall unstable and more likely to rupture.

    Another way of estimating the amount of inflammation in our arteries is with hs-CRP. Other issues can cause a rise in hs-CRP. However, in a patient who is at high risk of cardiovascular disease, I associate high levels of hs-CRP with being at very high risk for cardiovascular disease.

    So while traditional tests for cholesterol go some way to estimating cardiovascular risk, getting a much better estimation of risk requires a deep dive into different marke

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • The Mediterranean Diet for Preventing Heart Disease

    The Mediterranean Diet for Preventing Heart Disease

    “Diets, like clothes, should be tailored to you.” Joan Rivers

    According to Maimonides, a Philosopher born in Córdoba in what is now modern day Spain, “No disease that can be prevented by diet should be treated with any other means”. Although he lived almost a thousand years ago, there is more than a grain of truth in this statement. In her excellent TEDX talk, Dr Sarah Hallberg, makes a compelling argument that this is the case with Type 2 Diabetes. As the Medical Director of the Medically Supervised Weight Loss Program at IU Health Arnett, she is in a good position to know. 

    Now for the science bit…

    Unfortunately, a significant problem with any research into preventing disease is that it is inherently difficult to do. There are a number of reasons for this. Firstly, confounding factors play a big role. For example, a person who does one healthy behaviour – such as doing regular exercise – is more likely to eat a healthier diet. Researchers try to get around this by matching as closely as possible each group of participants in a study. However, it’s difficult to mitigate for everything. Secondly, it is hard to do dietary studies over a long period of time. Some people will drop out; some will get bored of the diet; some will make stuff up in their food diaries to keep the researcher happy. The latter is known as self-reporting bias. Thirdly, there is little money invested in finding out which broad diet might be the healthiest and good studies require lots of resources – and therefore lots of money. Many studies on diets are also prone to recall bias. This occurs with retrospective studies where two groups, one with a disease and one without, are asked to recall whether they ate lots of a certain food, say, cola bottle sweets. The researchers are hoping that those with the disease will say “Yeah, I ate loads of cola bottle sweets.” Then just before they publish their research paper they can hold a press conference and say “Cola bottle sweets cause disease X!”

    Recently, an article in the New England Journal of Medicine on the Mediterranean Diet gained a lot of media attention. For a number of reasons, this diet is worth close examination. The purpose of this study was primarily to test how good the Mediterranean Diet was in a head-to-head (also referred to as a randomised control trial) against a low fat diet in preventing heart disease, strokes, and deaths from all cardiovascular diseases (CVD) in otherwise healthy people. This is what is known as a primary prevention study. In contrast, a secondary prevention study would look at people who already had heart disease. The researchers also wanted to test whether two variations of the Mediterranean diet had any impact on health outcomes. One variation placed more importance on olive oil and the other placed more emphasis on nuts. So, these researchers were testing out Maimonides’ hypothesis – that a Mediterranean Diet can prevent heart disease and ultimately prevent the need for treatment by means other than diet.

    Who was in this study?

    One of the aspects that makes this study so interesting is the group of people the researches included. Although none of the participants had CVD when the study started, all of them had medical conditions or lifestyle behaviours that put them at high risk of CVD. The male participants were aged between 55-80 and the women between 60-80. This is an important point. If you are not over 55 and at high risk of CVD then the results are considerably less applicable to you. The researches likely chose patients who were at high risk of CVD for two reasons. Firstly, it is more likely that there will be a beneficial effect in people at higher risk. If they were doing this study in healthy people, they would have needed to enrol far more people to see any effect. Secondly, the people in this study – and in the population in general – really need an effective dietary intervention to prevent CVD. 

    A further important point that makes this study impressive is that as all the participants were unhealthy to begin with. Both the Mediterranean Diet and low fat diet were likely to be an improvement on what they were already eating. You might be thinking why, if the researchers want to get impressive results, did they not have one group of participants on their usual diet? This would have introduced what is known as performance bias. At the beginning and throughout the study, participants received coaching from dieticians. Participants also had assessments to check their adherence to the diet. Keeping people on their standard fare diet would have meant that they’d have received less attention than the other participants. Thus, they would have been at even more of a disadvantage. One source of performance bias that was present in the study was that the control group on the low fat diet received less coaching than the two Mediterranean Diet groups. 

    As I mentioned earlier, the goal of this study was to see the effect of a dietary intervention on an amalgamation of the number heart attacks, strokes, and deaths from all cardiovascular diseases. This is what is known as a composite end point. This study was geared from the outset to establish the effect of diet on this composite. 

    What was in the diet?

    One of the attractive aspects of the Mediterranean diet is – in my opinion – its simplicity. The dietary recommendations for the participants in the study were:

    Mediterranean Diet

    • Extra-virgin olive oil, greater than 4 tablespoons per day
    • Tree nuts and peanuts, greater than 3 servings per week
    • Fresh fruits, greater than 3 servings per day
    • Vegetables, greater than 2 servings per day
    • Fish, especially fatty fish such as tuna, salmon and mackerel, greater than 3 servings per week
    • Legumes (bean, peas and lentils), greater than 3 servings per week
    • Sofrito (diced carrots, celery, onions and garlic fried gently in extra-virgin olive oil) which forms the basis of many sauces in the Mediterranean, greater than 2 servings per week
    • White meat rather than red meat
    • Wine – yes, wine – with meals, greater than or equal to 7 glasses per week. This was optional for what the researchers called “habitual drinkers.”

    Foods that were discouraged included sweet fizzy drinks, commercial bakery goods, sweets and pastries, fat spreads and red and processed meats. 

    The low fat diet group were encouraged to eat:

    • Low fat dairy products
    • Breads, potatoes, pasta, and rice
    • Vegetables
    • Fresh fruit
    • Lean fish and seafood

    So who wins in the battle of Mediterranean vs Low Fat?

    For the composite end point I mentioned above, the Mediterranean diet resulted in a relative risk reduction of having either one of heart disease, strokes, and deaths from all cardiovascular diseases of 30%. A more useful way of looking at the data is numbers needed to treat. This tells us how many patients I would need to treat to prevent one person from getting one of the diseases in the composite end point. Crunching the numbers shows that, for the Mediterranean nut group, I would need to treat between 46-53 people to prevent one having heart disease, stroke, or death from any CVD; for the Mediterranean olive oil group, it is 56-232. 

    It is worth noting that in the subgroups that made up the composite, the two Mediterranean diets only showed a statistically significant benefit in reducing the number of strokes. However, remember the study was only powered to deliver a statistically significant result for the composite end point. 

    As mentioned early, dietary trials are difficult to do well. This trial is no different. The reason it gained press attention is that it was retracted and then republished. There were several reasons for the retraction. These included that some members of the same family were in the study but not randomised and that some people in the low-fat group ate a Mediterranean diet. After correcting for their errors, the researchers ran the analysis again and came to the same conclusion.

    Overall, the Mediterranean diet certainly shows some benefit in preventing CVD for people who are at risk. This study is certainly an important one. However, it is one of several that confirm the benefits of a Mediterranean diet. So if this diet appeals to you and is aligned with your dietary beliefs I think it is the optimal diet for health. A diet needs to align with your beliefs for you to stick with it. Hence, diets should be, to an extent, personalised. Diet is, though, only part of the picture. It is likely that the reason for longevity in so many Mediterranean communities is a composite. In addition to diet, daily exercise, fasting, sense of community and socialisation, spirituality, sunshine and clean air all contribute.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.