Tag: Healthy Ageing

  • What your mouth can tell you about your health

    What your mouth can tell you about your health

    Most people think of oral health as something their dentist handles. Bleeding gums, cavities, the occasional check-up. What most people do not know is that the health of your mouth has a direct and well-evidenced connection to your heart, your immune system, and your metabolic health. What happens in your mouth does not stay there.

    The bacteria that cause gum disease do not simply sit in your gums. They enter your bloodstream. They have been found inside the walls of arteries. They trigger inflammatory signals that affect your heart, your blood sugar, and your immune response. Research shows that treating gum disease reduces a key marker of systemic inflammation by an amount comparable to some dedicated lifestyle interventions. This is not a fringe idea. It is increasingly recognised as one of the most overlooked connections in medicine.

    At Coyne Medical, we include an oral health screen as part of the Ultimate Health Screening for exactly this reason. This guide explains what the test looks at, what the results mean, and why your mouth is worth including in any serious health assessment.

    What the oral health screen measures

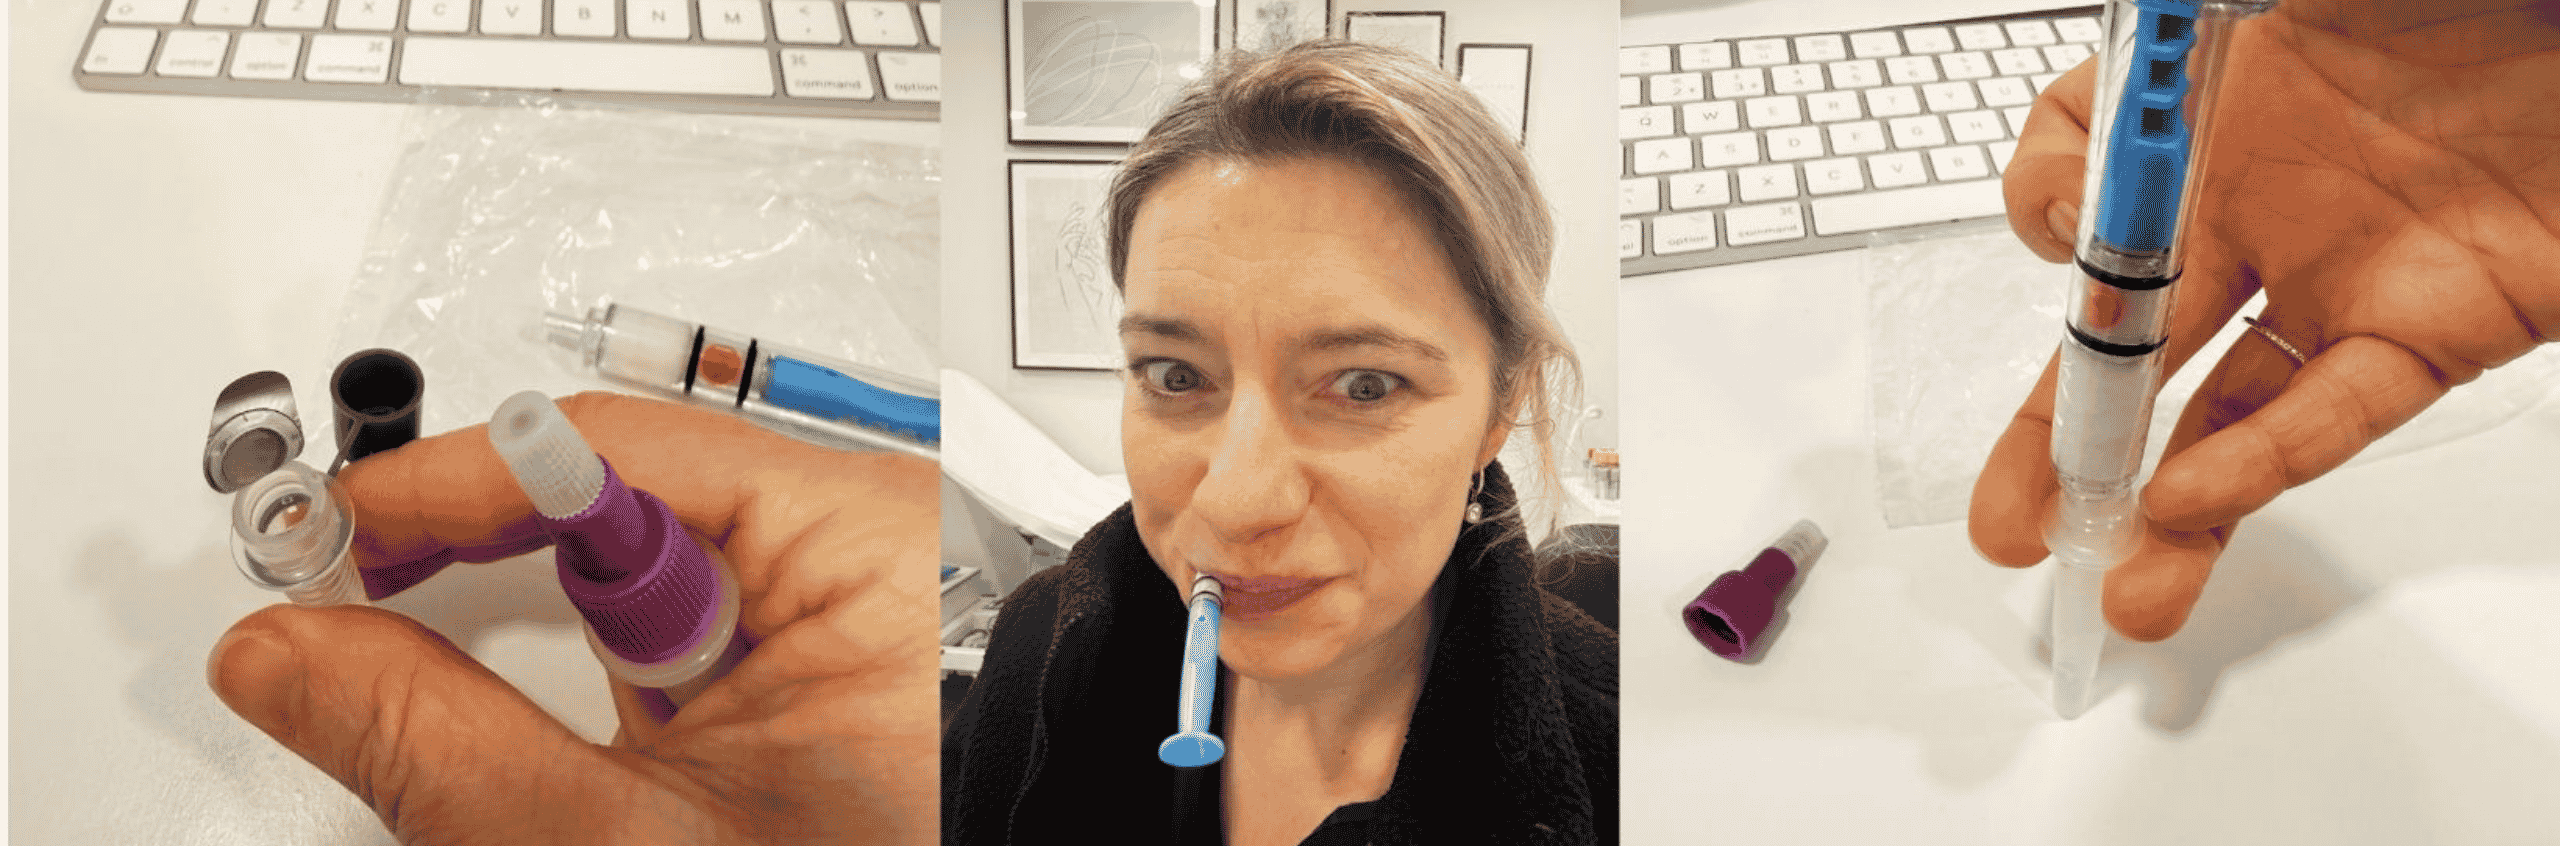
    The test is simple. During your GP assessment, we use a small cotton swab to collect a saliva sample. That sample is then applied to a test card and analysed on the spot. No laboratory, no waiting weeks for results. The findings feed directly into your overall results consultation.

    The sample is measured across seven markers.

    P. gingivalis is the main bacterium responsible for gum disease. It is also the organism most directly linked to cardiovascular and gut consequences of oral inflammation. Researchers have found it not just near arterial plaques but inside them. The test shows whether levels are within the good range, poor, or very poor.

    MMP-8 is an enzyme your immune system releases when gum tissue is under attack. Raised levels indicate active inflammation in the gums, often before you have noticed any symptoms yourself.

    Salivary pH measures how acidic your mouth is. A pH between 6.5 and 8.5 supports a healthy balance of bacteria. A more acidic environment lets harmful bacteria thrive and protective ones retreat.

    Buffering capacity is your mouth’s ability to neutralise the acids that bacteria produce. When this is low, the risk of enamel erosion increases and the conditions for an imbalanced bacterial environment are in place.

    Nitric oxide is a molecule that plays a role in keeping blood vessels healthy and blood pressure regulated. Part of it is produced through activity in the mouth, which makes salivary nitric oxide a useful window into cardiovascular and metabolic health.

    Salivary proteins are part of your mouth’s first line of defence against infection and inflammation. Low levels suggest that defence is reduced.

    Salivary glucose, a good picture of metabolic health.

    All seven results are reviewed by your Coyne Medical GP alongside your cardiovascular markers, metabolic blood results, and full clinical picture. That is what makes the findings meaningful rather than just numbers on a page.

    Why oral health affects the rest of your body

    Your heart

    Gum disease increases the risk of coronary heart disease by roughly 25 to 35 percent. The bacteria responsible for gum disease can enter the bloodstream through inflamed gum tissue and travel to the arteries, where they contribute to the build-up of plaques. They also trigger the production of inflammatory molecules that drive that process further. These are the same inflammatory signals that cardiologists spend significant effort trying to reduce.

    Studies have shown that treating gum disease lowers a widely used marker of inflammation in the body by a meaningful amount after six months of treatment. That is a real clinical effect from addressing something that needed treating anyway.

    Your blood sugar

    The relationship between gum disease and type 2 diabetes runs in both directions. High blood sugar creates an environment in which harmful oral bacteria thrive. And in turn, chronic inflammation from gum disease makes it harder for the body to regulate blood sugar effectively. Treating gum disease has been shown to improve blood sugar control in people with type 2 diabetes. The mouth is part of the metabolic picture.

    Your immune system

    Your mouth is home to over 700 species of bacteria, making it the second most diverse microbial environment in the body after the gut. When that balance tips toward a harmful mix, the effects do not stay local. You swallow around 1.5 litres of saliva every day, and whatever bacteria are living in your mouth travel with it. Harmful oral bacteria have been found in inflamed gut tissue. Chronic oral inflammation also primes immune cells in ways that can amplify inflammatory responses throughout the body.

    Understanding your results

    Each of the seven markers is rated across a range from good to very poor, with reference values in the report. A result outside the optimal range is not a diagnosis. It is a signal worth understanding in the context of everything else your health screen has found.

    Some patterns that commonly come up and what they tend to suggest:

    Elevated P. gingivalis alongside raised inflammatory markers elsewhere in the blood results points toward gum disease as an active contributor to systemic inflammation. The starting point is almost always a dental review and professional periodontal assessment.

    Low buffering capacity combined with a poor salivary pH often reflects frequent consumption of acidic foods or drinks, and can also indicate dehydration or mouth breathing, both of which carry broader health implications worth discussing.

    Low nitric oxide, particularly alongside elevated blood pressure or cardiovascular risk markers, adds a useful piece to the cardiovascular picture. Increasing dietary nitrate through vegetables has good evidence in this context and is something your GP can discuss with you at the results consultation.

    Low salivary proteins can reflect immune suppression, chronic stress, or nutritional factors. It is most useful when considered alongside the full screening picture rather than in isolation.

    High salivary glucose levels match closely to your blood glucose levels, we can correlate these with your blood results.

    What happens next

    Where all six markers are within normal ranges, no specific action is needed beyond maintaining good oral hygiene and seeing your dentist regularly.

    Where results fall outside optimal ranges, your Coyne Medical GP will discuss the findings at your results consultation. Depending on what is found, this may include a referral to a dentist or periodontist for professional assessment, dietary changes targeting specific markers, further investigation of relevant blood markers, or a follow-up review at three to six months.

    The oral health screen does not replace dental care. Its role is to make sure that meaningful signals in your mouth are not missed in the gap that tends to exist between medical and dental medicine

    Frequently asked questions

    Is the oral health screen a dental test? No. It is a health screen that uses saliva to look at markers connected to cardiovascular risk, inflammation, and metabolic health. It complements your dental care but does not replace it. All results are reviewed by a Coyne Medical GP, not a dentist.

    Do I need to have gum disease for this to be relevant to me? No. Many people with elevated oral inflammatory markers have no symptoms at all. The test is most valuable as part of a comprehensive health screen precisely because it can identify signals before they become visible problems.

    Why is this test included in the Ultimate Health Screening? Oral health is one of the most well-evidenced and most overlooked contributors to cardiovascular risk and systemic inflammation. Including it within a comprehensive screen allows the findings to be interpreted alongside cardiovascular, inflammatory, and metabolic data, which is where the clinical value lies.

    What is P. gingivalis and why does it matter? It is the main bacterium responsible for gum disease, and the one most directly linked to effects beyond the mouth. It has been found inside arterial plaques and in inflamed gut tissue. Most people have never heard of it, but it is one of the more significant organisms in the body from a systemic health perspective.

    Will my results be shared with my dentist? Not automatically. The report belongs to you, and many patients choose to share it with their dentist as a starting point for a conversation about their gum health. Your Coyne Medical GP can help you understand what to share and how.

    Is a saliva test accurate enough to be clinically useful? The test measures specific biochemical markers directly from saliva and is designed for use in clinical settings. It does not replace a full laboratory periodontal analysis, but as a systemic risk indicator within a comprehensive health screen and interpreted by a GP alongside other clinical findings, it provides genuinely useful information.

    A note from Dr Lucy Hooper

    Medicine and dentistry are treated as separate disciplines, but the biology does not respect that division. Your gut begins in your mouth. Inflammatory signals from your gums enter your bloodstream. Bacteria from your oral environment travel to your arteries and your gut. Yet in most medical settings, the mouth is simply not examined.

    We added the oral health screen to the Ultimate screening because we want to close that gap. Not to become dentists, but to make sure that when we are reviewing someone’s cardiovascular risk or their inflammatory markers, we are not ignoring something significant and treatable happening upstream. For some patients, what we find in their saliva will be the most actionable result in the whole screen.

    Discover the Ultimate Health Screening

    The oral health screen is one part of the Coyne Medical Ultimate Health Screening. It sits alongside whole body MRI, VO2 max testing, pharmacogenomics, a 55 gene inherited cancer risk panel, and a full advanced blood panel. Find out what is included and how to book.

    British Society for Genetic Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in BBC, The Guardian, Women’s Health, The Times and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.


  • Can You Still Eat Beef and Be Heart Healthy?

    Can You Still Eat Beef and Be Heart Healthy?

    Is beef heart healthy? Red meat has had a rough ride in recent decades. It’s been linked to everything from heart disease to early death, with no shortage of headlines declaring it public enemy number one. But a recent meta-analysis has taken a more measured look at one particular type of red meat: lean, unprocessed beef.

    The study examined 20 randomised controlled trials (RCTs) involving over 1,000 adults. Researchers focused on key cardiovascular disease (CVD) risk factors, including blood lipids like LDL and HDL cholesterol, triglycerides, and blood pressure. Essentially, the study found that beef is not quite the villain it’s made out to be.

    What the Study Looked At

    This was a systematic review and meta-analysis. A trial design that is about as robust as nutritional evidence gets. Researchers pooled data from high-quality trials that compared diets with varying amounts of lean beef. The aim was to isolate beef’s impact on heart health. The study aimed to avoid the usual confusion that comes from lumping it together with other red meats or with heavily processed sausages and burgers.

    Most participants were either healthy or had common metabolic issues such as high cholesterol or type 2 diabetes. The average beef intake in the high-beef groups was around 160 grams per day, roughly two servings. Which, in my opinion, is quite a lot of beef. Comparators were diets with little or no beef.

    The Verdict on Cholesterol and Blood Pressure

    The key takeaway was that eating lean, unprocessed beef had no meaningful impact on most heart health markers.

    Total cholesterol, HDL and triglycerides stayed broadly the same, regardless of how much beef people ate. Both systolic and diastolic blood pressure also remained broadly unchanged. There was a very small increase in LDL cholesterol, around 2.7 mg/dL or 0.07mmol/L. This might sound concerning. However, this is a trivial increase. For context, that’s the kind of variation you might get from eating a slightly different breakfast.

    Even this tiny effect on LDL was mostly driven by one influential study. When that study was removed in a sensitivity analysis, the difference disappeared.

    It is also worth noting that lean beef tends to be higher in cholesterol-lowering fats (monounsaturated and polyunsaturated) than cholesterol-raising saturated fats. Many of the included trials also tried to match saturated fat across diets. This makes it unlikely that saturated fat was a major driver.

    So, Is Beef Heart Healthy?

    The answer, based on this analysis, is that it is certainly not harmful. At least not in the form studied here. Eating lean, unprocessed beef in moderate amounts does not appear to harm cholesterol levels or blood pressure. In fact, it can be a useful source of high-quality protein, iron, zinc, and vitamin B12. These are nutrients that many people are deficient in.

    Of course, this does not mean you should eat steak every day and skip the vegetables. A balanced diet is still key, and occasionally swapping beef for fish or plant-based proteins is still a good idea. But the idea that any amount of beef will clog your arteries and cut your life short is not supported by this data.

    But What About the Funding?

    Yes, the study was funded by the Beef Checkoff, an industry body. That should always raise eyebrows. However, the researchers clearly disclosed this. The study used rigorous methods and followed gold-standard protocols like PRISMA. In fact, over 70 per cent of the industry-funded trials included were rated as low risk of bias. That was better than some of the non-industry-funded ones.

    This does not mean we take the results at face value without scrutiny. However, we should be cautious about dismissing them just because of who paid for the research. The rigour was there.

    Where This Leaves Us

    Nutritional science is messy, and red meat is a prime example. Much of the scare comes from observational studies that cannot separate diet from lifestyle. People who eat lots of red meat often do fewer healthy things overall. They tend to exercise less, smoke more, and eat fewer vegetables. That makes it tricky to tease out cause and effect.

    What this meta-analysis gives us is a cleaner look at the question. And the answer, at least for lean, unprocessed beef, appears to be that there is no major impact on lipids or blood pressure. It is important to mention that this study did not look at hard outcomes. It did not, for example, tell us whether people who ate more lean beef were more likely to die or a heart attack or stroke. It merely points out that people who ate lean beef had no change in the risk factors for heart disease and stroke. 

    If you enjoy beef, there is no need to swear it off entirely. Choose lean cuts, don’t char it to oblivion, and pair it with plenty of plant-based foods. A steak night now and then, as part of an overall healthy lifestyle, is unlikely to be the thing that tips the balance.

    Nutrition is full of strong opinions. But evidence beats ideology. This latest study adds a little sanity back into the red meat debate. It is not a green light to live on burgers, but it is a reminder that context, portion size, and overall diet quality matter far more than demonising single foods.

    And if someone tries to guilt you over your Sunday roast, you now at least have a well-referenced comeback.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.
  • A Closer Look At Calcium Supplements

    A Closer Look At Calcium Supplements

    Humphrey Davey wanted to study medicine. He was an apprentice to a surgeon and apocathery. But Davey never did study medicine. Instead, he became a self-taught chemist and he discovered several elements including calcium.

    The narrative surrounding calcium supplementation is as complex as it is fascinating. Calcium supplementation has roots deeply embedded in both science and societal beliefs. Calcium, the stalwart of bone health, has been championed for decades as a critical component of a healthy lifestyle. This has been particularly the case in improving bone health. This belief has not only permeated clinical guidelines but also the public consciousness. Consequently, a significant portion of the population, especially older women, incorporate calcium supplements into their daily regimen. In the United States alone, a striking 61% of women over 60 were taking calcium supplements between 2003 and 2006. This widespread adoption has catapulted calcium supplementation into a billion-dollar industry. Millions of people across various age groups seek to bolster their health through calcium supplements.

    Are Calcium Supplements Safe?

    Yet, the message of “more calcium equals better health” is increasingly being questioned. Initial studies posited that dietary calcium had a more pronounced effect on bone building compared to its supplemental counterpart. This is presumably due to its better absorption. Yet, the reality of dietary habits and the availability of calcium-rich foods means not everyone can achieve sufficient calcium intake through diet alone. All the more so with the recent trend towards milk substitutes. This underscores a potential role for supplementation in cases of dietary inadequacy.

    But as the practice of calcium supplementation has grown, so too have concerns about its safety. Recent years have seen a burgeoning debate. The discourse has been fueled by studies suggesting potential risks associated with indiscriminate calcium supplementation. Notably, a meta-analysis by Bischoff-Ferrari et al. highlighted an increased risk of hip fractures. A review of randomised clinical trials found that calcium supplementation did not correlate with a reduced risk of fractures among older adults. So, there was certainly evidence to suggest an either negative or at best neutral effect of calcium supplements on the risk of hip fractures. Remember, the main reason to take calcium is to avoid a devastating hip fracture. However, this discourse took a more concerning turn than merely suggesting a lack of benefit. Other findings suggested a significant increase in cardiovascular disease associated with calcium supplements. This was particularly the case in men.

    Are Calcium Supplements Harmful?

    Amidst this backdrop, the recent findings from a study leveraging the expansive UK Biobank dataset provide a nuanced perspective on the intersection of calcium supplementation and cardiovascular health. The research examined the associations between calcium supplementation and cardiovascular disease (CVD) events and mortality. In particular, it examined supplementation in individuals with and without diabetes. The results painted a stark picture for those with diabetes. Regular calcium supplement intake was linked to higher risks of heart disease and death in diabetics. No significant risk increase was observed in participants without diabetes.

    This dichotomy between individuals with and without diabetes underscores the need for a more tailored approach to calcium supplementation. It also challenges the prevailing “one-size-fits-all” mentality. The study’s implications are profound. It suggests healthcare providers weigh the potential adverse effects of calcium supplements against their benefits, particularly among diabetic patients.

    The dialogue surrounding calcium supplementation, once dominated by an uncritical endorsement of its benefits, is evolving. It calls for a reevaluation of how we perceive and prescribe these supplements. I would advocate for a balance that prioritises dietary sources of calcium. Supplementation should be recommended judiciously. The study serves as a reminder of the importance of personalised healthcare and the value of diet over supplements.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Tomatoes: A Natural Way To Improve Blood Pressure

    Tomatoes: A Natural Way To Improve Blood Pressure

    In the world of nutritional science, we often see people narrow focus to single nutrients. While I’m generally not a fan of this approach, a recent study on tomatoes and their potential to combat high blood pressure has caught my attention, and it’s really quite compelling.

    The PREDIMED Study: Tomatoes Blood Pressure Benefits

    The PREDIMED trial is an exploratory analysis involving 7,056 participants who have high blood pressure. It delivered some fascinating insights into the role of tomatoes in managing blood pressure. Who knew that these red fruits, often mistaken for vegetables, could improve cardiovascular health?

    Tomatoes vs. Hypertension: What the Data Says

    Participants in the study were grouped based on their tomato consumption, from the least (<44 g) to the highest (>110 g). Over three years, those with the highest intake showed a remarkable 36% reduction in the risk of developing hypertension compared to those who ate the least.

    The Science Behind the Scenes

    The secret sauce here seems to be lycopene, a potent antioxidant found abundantly in tomatoes. Around 85% of our lycopene intake comes from tomatoes and their derivatives. Lycopene is excellent at neutralising free radicals – those unstable molecules that cause cellular damage and contribute to various health issues, including hypertension.

    Lycopene’s Broader Impacts

    Beyond just mopping up free radicals, lycopene also plays a role in inhibiting the ACE enzyme, which is involved in blood pressure regulation. This dual action of lycopene not only helps in reducing hypertension but also has implications for broader cardiovascular health.

    Alternatives to Tomatoes for Lycopene Intake

    If you’re not a tomato fan, don’t worry. Lycopene is also found in pink grapefruits, pink guavas, watermelons, and papayas. Even processed tomato products like sauces and ketchups are rich in lycopene. The key is to find a balance that suits your palate and dietary preferences.

    The Takeaway: A Step Towards Better Health

    This study reiterates the age-old wisdom about eating fruits and vegetables, with a spotlight on tomatoes. Incorporating them into our diet, provides be a simple yet effective way to manage blood pressure and improve heart health.

    It’s important to remember that nutrition is more complex than single nutrients. But this study on tomatoes and lycopene presents an opportunity to make an impact reducing hypertension rates.

    So next time you’re contemplating your meal choices, remember that adding a splash of red might just be what your heart needs. 

    If you found this blog helpful we would love you to share it with your friends and family

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.
  • Lipid-Lowering Therapy in Older Adults: A New Danish Study Sheds Light

    Lipid-Lowering Therapy in Older Adults: A New Danish Study Sheds Light

    There’s been a longstanding debate about the effectiveness and necessity of lipid-lowering therapies, especially statins, in older adults. A recent Danish cohort study involving 65,190 individuals aged 50 and above has provided some illuminating insights into this topic. The rates of use of statin therapy has been shown to decline in people above age 75. This applies even to people who are known to have cardiovascular disease. The decline in statin usage is even more sharp in those who do not have cardiovascular disease.  

    The Conventional Wisdom and the Emerging Data

    Traditionally, the focus of lipid-lowering therapy, particularly aiming to reduce low-density lipoprotein cholesterol (LDL-C), has been on younger populations. But does this mean our approach should differ as we age? This study suggests perhaps not.

    What the Study Reveals

    The Danish research team embarked on an observational study using national healthcare and administrative registries to understand the impact of initiating lipid-lowering treatments in older adults. Their findings:

    * Substantial Risk Reductions: For each 1mmol/L reduction in LDL-C, there was a 23% decreased risk of major vascular events, regardless of whether individuals were older or younger than 70.

    * Uniform Benefits Across Ages: These benefits were consistent in both the older (≥70 years) and younger (<70 years) groups, indicating that age does not diminish the effectiveness of these therapies.

    * Supportive Observational Data: Complementing this data are findings from Giral and colleagues, who observed lower rates of cardiovascular events in those who continued statin treatment past the age of 75, compared to those who stopped. It included people who had taken statins regularly but hadn’t had heart problems before. The study found that stopping statins increased the risk of hospital admission for heart issues by 33%.

    Broader Implications and Future Directions

    This study aligns with data from the Cholesterol Treatment Trialists Collaboration and other primary prevention trials. The Cholesterol Treatment Trialists Collaboration has been running since 1994. It conducts meta-analyses of cholesterol intervention trials. The Collaborations aims to assess whether interventions on lipid-lowering work in different types of people. A meta-analysis allows a more reliable assessment of the effect of an intervention than a single trial alone. Previously, they have demonstrated that statin therapy does not increase the risk of cancer or of other non-cardiac causes of death. The key takeaway is that lowering LDL-C levels is crucial for reducing cardiovascular risk, regardless of age.

    Two prospective randomised trials are also on the horizon, promising to provide more clarity on this topic for older adults. These include the STAREE study, focusing on patients over 70, and the SITE/SAGA study, examining statin cessation in individuals 75 years or older. While we now have some clarity for over 50s, there is still debate as to whether statins are useful and cost-effective for over 75s. These two studies should provide some clarity.

    My Perspective

    The message here is clear: preventing cardiovascular events is a universal goal, transcending age barriers. These new findings reinforce the importance of managing cholesterol levels even in older adults. It’s not about the number of candles on a birthday cake; it’s about the numbers that count for heart health. 

    For our younger patients, it’s important not to delay statin treatment. A study in the journal  Circulation analysed data to uncover when younger adults should start statins to prevent heart disease over 30 years. It found that starting cholesterol-lowering treatments in your 40s, especially if your LDL is high, could significantly reduce the risk of heart disease later on. This study suggests it might be more important to decide when to start treatment rather than if you should start at all.

    Make sure you have your discussed your risk of cardiovascular disease and discussed a plan to lower your risk with your GP.

    Please help another person improve their heart health by sharing this blog.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Does Salt Intake Affect Blood Pressure? New Insights from a Groundbreaking Study

    Does Salt Intake Affect Blood Pressure? New Insights from a Groundbreaking Study

    In the ever-evolving world of dietary recommendations, the role of sodium in blood pressure management has been a subject of fierce debate. A recent study, conducted across two US cities with 213 participants aged 50 to 75, sheds new light on this topic. It is especially useful for those on blood pressure medications.

    Understanding the Sodium-BP Connection

    The study aimed to explore the individual blood pressure response to dietary sodium intake. It analysed variations based on baseline blood pressure and antihypertensive medication usage. The participants, including those with normal blood pressure, controlled, uncontrolled, and untreated high blood pressure, were put on high- and low-sodium diets in a crossover design.

    Dietary Intervention: High vs. Low Sodium

    Participants first adhered to their usual diet, followed by one-week phases of high-sodium (about 2200 mg added daily) and low-sodium (totaling about 500 mg daily) diets. The primary focus was on changes in 24-hour ambulatory systolic and diastolic blood pressure, mean arterial pressure, and pulse pressure.

    Key Findings: A Shift in Blood Pressure

    The results were revealing:

    • Median Blood Pressure Changes: On usual, high-sodium, and low-sodium diets, the median systolic blood pressures were 125, 126, and 119 mm Hg, respectively.
    • Mean Arterial Pressure: The median change in mean arterial pressure between high- and low-sodium diets was 4 mm Hg, significant across all hypertension statuses.
    • Salt Sensitivity: Using the threshold of a 5 mm Hg or greater decline in mean arterial pressure, 46% of participants were classified as “salt sensitive.”

    Consistency Across Subgroups

    Interestingly, the blood pressure decline from a high- to low-sodium diet was consistent across various subgroups, including age, sex, race, hypertension status, baseline BP, diabetes, and body mass index. This suggests that dietary sodium reduction may be beneficial for a wide range of individuals.

    Conclusions: A Relevance for All

    This study reinforces the idea that reducing dietary sodium can significantly lower blood pressure in middle-aged to elderly adults. The reduction in blood pressure was independent of original blood pressure status and blood pressure medication use. This finding is particularly relevant for those seeking non-pharmacological methods to manage blood pressure.

    My Takeaway

    Reducing sodium intake isn’t just for select groups; its benefits extend broadly, offering a universally applicable approach to better blood pressure management. Of course not everyone is a “salt-responder” but if you suffer from high blood pressure then reducing dietary sodium is well worth as try.

    Please help someone else by sharing this blog. 

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Minerals and Mood

    Minerals and Mood

    Most of us are continuously juggling multiple roles and responsibilities and hence it’s easy to overlook something as basic as our dietary habits. However, a recent study showed some fascinating insights that suggest that, from a mental health point of view, our meal choices can be incredibly influential. 

    A Deep Dive into Dietary Minerals and Depression

    A comprehensive analysis involving over 20,000 participants from the National Health and Nutrition Examination Survey (2007-2018) brought to light the complex relationship between nine key dietary minerals and depressive symptoms. These minerals studied were:

    • Calcium (Ca)
    • Phosphorus
    • Magnesium (Mg)
    • Iron (Fe)
    • Zinc
    • Copper (Cu)
    • Sodium
    • Potassium (K)
    • Selenium (Se)

    The study employed sophisticated statistical models (such as the Bayesian kernel machine regression) to assess the impact of these minerals on depression, measured by the Patient Health Questionnaire-9 (PHQ-9) scores. This is a standard tool used in primary care to quantify the extent of patients’ depression. 

    It’s Not Just What You Eat, But How They Interact

    The results were intriguing:

    • Negative Association That’s Positive: A higher intake of these minerals was linked to lower PHQ-9 scores, indicating fewer depressive symptoms.
    • Role of Selenium and Potassium: Selenium emerged as the key player, showing the most significant impact, closely followed by potassium.
    • Interactions Matter: Interactions between certain minerals, like calcium and iron, also influenced depressive symptoms.
    • Gender-Specific Effects: Interestingly, copper showed a more pronounced effect in females.

    What Does This Mean for Us?

    This study adds to the growing body of evidence suggesting that our diet, specifically mineral intake, plays a significant role in mood regulation. Minerals are not just building blocks for our bodies; they are crucial for the synthesis of mood-regulating neurotransmitters like serotonin and dopamine.

    So, What Can We Do?

    Here’s a quick guide to foods rich in these crucial minerals:

    • Nuts and Seeds: A treasure trove of selenium, especially Brazil nuts. These are are great for reducing the risk of cardiovascular disease
    • Eggs: Dubbed nature’s multivitamin. Don not worry about the Mapco of eggs on cholesterol. 
    • Cruciferous Vegetables: Such as broccoli, cabbage, and Brussels sprouts.
    • Beans: High in fibre and a useful source protein (the bean soup at la Pizzica deli is highly recommended as the source of beans!).
    • Avocados and Berries: These are rich in omega-3 fatty acids and essential minerals.
    • Leafy Greens: Folate-rich and which is important for nutrient transport to the brain.
    • Shellfish and Sardines: High in zinc and omega-3s.

    A Note on Supplementation

    While a balanced diet is the gold standard, some patients, especially those facing severe mental health challenges, might find it difficult to maintain such a diet. In these cases, a multimineral supplement might be  helpful

    We’re here not just to treat but to educate and empower. This study offers a glimpse into the significant impact of diet on mental health. Try to embrace these findings in your culinary choices. And, as always, we’re here to guide you on this journey towards a healthier, happier you.

    P.S. For personalised advice on nutrition and mental health, to check your nutrient levels or to discuss this study further, feel free to book an appointment. 

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.

  • Knee Osteoarthritis Treatment: The Role of Hyaluronic Acid Injections and Ultrasound Guidance

    Knee Osteoarthritis Treatment: The Role of Hyaluronic Acid Injections and Ultrasound Guidance

    Knee osteoarthritis (OA) is a degenerative joint disease that affects millions. The search for effective treatments has been ongoing, with intra-articular hyaluronic acid (IAHA) injections, such as Ostenil Plus and Durolane, emerging as promising options. However, there’s a discrepancy between the medical evidence backing IAHA and the varied recommendations from international guidelines. So, how effective really is this treatment, and does the method of injection play a role in its success?

    The Promising Potential of IAHA Injections for Knee OA

    Recent studies have focused on analysing the benefits and safety of IAHA injections. A comprehensive literature review, including randomized controlled trials and meta-analyses, highlighted the following:

    • Symptomatic Relief: IAHA, including Ostenil Plus, offers moderate relief to those with knee OA without significant safety concerns.
    • Impressive Benefit/Risk Ratio: When looking at improvements in knee OA outcomes, IAHA might have one of the best benefit-to-risk ratios among pharmacologic options. Notably, patients experience an overall increase in quality-adjusted life years and significant delays in needing total knee replacement.

    In light of these findings, it’s worth considering IAHA injections as a viable treatment option. However, the real game-changer might be in tailoring treatments by the stage of disease and specific patient characteristics. The future of IAHA treatment may involve identifying OA patient subgroups that show a more pronounced response to the treatment. Combining IAHA with other treatments might also offer optimised care for knee OA patients.

    Optimising Treatment with Ultrasound Guidance

    Viscosupplementation involves injecting hyaluronic acid into the knee. It has faced criticism due to inconsistent pain relief benefits. One major concern has been the accuracy of needle placement, especially in obese patients. Enter ultrasound (US) guidance.

    A study analysed community-dwelling patients receiving HA knee injections, comparing outcomes between those getting injections with traditional landmark guidance and those with US guidance. The results were compelling:

    • Similar Patient Cohorts: Both the US-guided and landmark-guided patient groups had similar demographics and arthritis severity.
    • Surgery-Free Outcomes: A significant number of patients in the landmark-guided group (45.8%) required knee arthroplasty (surgery), compared to only 33.2% in the US-guided group. The difference was even more pronounced among obese patients, with 51.8% in the landmark-guided group requiring surgery compared to 34.8% in the US-guided group.

    These findings suggest a clear conclusion: To optimise the benefits of viscosupplementation, ensuring accurate intra-articular needle placement via US guidance is crucial. When done right, patients receiving US-guided HA injections are less likely to require subsequent knee surgeries.

    In Conclusion

    Knee osteoarthritis is a challenging condition, but modern treatments like IAHA injections offer hope. When combined with advanced techniques like ultrasound guidance, these treatments can provide significant relief and improve the quality of life for many patients.

  • Unleashing the Power of High-Intensity Exercise: Insights from the CENIT Trial

    Unleashing the Power of High-Intensity Exercise: Insights from the CENIT Trial

    Exercise has long been recognised as a key factor in maintaining a healthy heart and reducing the risk of coronary artery disease (CAD). A recent study called the CENIT trial has provided some valuable insights into the benefits of high-intensity interval training (HIIT) for patients with established CAD. Published in the European Journal of Preventive Cardiology, this research reveals how HIIT can counteract disease progression and promote cardiovascular health. 

    Coronary artery disease occurs when atherosclerosis, or plaque, builds up in the arteries that supply blood to the heart. Over time, plaques can increase in volume and become unstable and rupture leading to a stroke or a heart attack. Atheroma volume, which measures the amount of plaque present in the arteries, is a crucial indicator of CAD severity and has been shown to increase the likelihood of future cardiac events.

    To better understand the impact of exercise on CAD, let’s examine the exercise interventions in the CENIT trial. The study consisted of two groups: the high-intensity interval training (HIIT) group and the control group. Each group had a specific exercise program.

    1. High-Intensity Interval Training (HIIT) Group: Participants in the HIIT group engaged in two supervised exercise sessions per week for a duration of 6 months. Each session began with a 10-minute warm-up at a moderate intensity (around 60% to 70% of peak heart rate). This was followed by four intervals of intense exercise, lasting for four minutes each, at an intensity of 85% to 95% of peak heart rate. Active recovery periods, lasting for three minutes at a moderate intensity, were included between intervals. The sessions concluded with a 5-minute cooldown period. The HIIT sessions involved activities such as walking or running on a treadmill, bicycling, or other exercises that engaged large muscle groups. Participants were encouraged to use a wearable device to track their heart rate and activity levels during the HIIT sessions. This allowed them to maintain the desired intensity and monitor their progress. In addition to the supervised sessions, participants were advised to engage in home-based endurance training. This included performing intervals and any other physical activities that involved dynamic work with large muscle groups.
    2. Control Group: The control group followed contemporary preventive guidelines for physical activity without receiving further supervision. They were encouraged to engage in regular physical activity of moderate intensity for 30-60 minutes on more than 5 days per week. Not only was this exercise not supervised but it was not monitored unlike in the intervention group.

    The CENIT trial focused on the effects of supervised HIIT on coronary plaque geometry in patients with stable CAD who had undergone percutaneous coronary intervention (PCI). Here’s what they found:

    1. Regression of Atheroma Volume: Patients who participated in 6 months of supervised HIIT experienced significant regression in atheroma volume compared to those following standard preventive guidelines. This means that the plaque buildup in their arteries was reduced, potentially lowering their risk of future coronary events.
    2. Improved Cardiorespiratory Fitness: The HIIT group exhibited a significant improvement in peak oxygen consumption (VO2peak), which measures cardiorespiratory fitness. By increasing VO2peak, HIIT enhances the overall health of the cardiovascular system.
    3. Positive Body Composition Changes: Patients in the HIIT group also experienced reductions in body mass index (BMI) and waist circumference. These improvements in body composition are important markers of metabolic health and can contribute to a reduced risk of CAD and related complications.

    The findings from the CENIT trial provide reasonable evidence for the effectiveness of HIIT in managing CAD and improving cardiovascular health. It is, however, difficult to tease out from the study whether it was the supervision of exercise, or wearing a monitor that someone else was tracking or the HIIT that had the greatest benefits. Based on these results, here are some key takeaways to consider:

    1. Consult An Experienced Personal Trainer: If you have established CAD or are at risk for heart disease, consult a very experienced personal trainer who is confident in managing patients who have stable heart disease. They can provide personalised recommendations based on your health status and previous exercise experience.
    2. Embrace High-Intensity Interval Training (HIIT): Consider incorporating supervised HIIT sessions into your exercise routine under professional supervision. HIIT involves short bursts of intense exercise alternated with active recovery periods, making it an efficient and time-effective workout option. But note, the intervention group did not just do HIIT, they also did low-intensity exercise. 
    3. Prioritise Exercise: HIIT’s positive impact on atheroma volume regression, improved cardiorespiratory fitness, and positive body composition changes highlight the importance of exercise as a core component of cardiac rehabilitation programs. When compared to another study looking at the effects of high-intensity statin on plaque lipid volume, high-intensity exercise combined with low-intensity exercise had an effect comparable effect to that of a high-intensity statin.
    4. Monitor Your Exercise: The intervention group wore a wearable and knew they were being monitored. Use a wearable and get an accountability partner to keep you on track. 

    The CENIT trial provides evidence that high-intensity interval training, supervised by a personal trainer and the wearing of a fitness tracker can effectively counteract disease progression and improve cardiovascular health in patients with established coronary artery disease. Participating in supervised HIIT sessions can lead to a reduction in atheroma volume, improved cardiorespiratory fitness, and positive body composition changes.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.
  • Trucheck™ vs. Galleri®: Comparing Advanced Blood Tests for Early Cancer Detection

    Trucheck™ vs. Galleri®: Comparing Advanced Blood Tests for Early Cancer Detection

    Introduction – The Future of Cancer Screening with Advanced Blood Tests

    Cancer screening has taken a significant leap forward with the introduction of advanced blood tests like Trucheck™ and Galleri®. These innovative screening methods aim to detect cancer at its earliest stages, providing vital information for timely interventions and improved outcomes. In this blog, we will compare Trucheck™ and Galleri®, exploring their scientific principles, advantages, and considerations, to help you make informed decisions about cancer screening.

    How Do Trucheck™ and Galleri® Blood Tests Work?

    Trucheck™ – Detecting Circulating Tumor Cells (CTCs)

    Trucheck™, developed by Datar Cancer Genetics, focuses on detecting circulating tumour cells (CTCs) and circulating ensembles of tumour-associated cells (C-ETACs) in peripheral blood samples. By employing primary negative enrichment, Trucheck™ enables the survival of malignant cells while allowing non-malignant cells to undergo apoptosis (programmed cell death). The subsequent analysis of tissue-specific markers on these cells helps identify cancer types and their likely organ of origin. Trucheck™ offers high sensitivity, specificity, and an overall advantage in detecting over 70 solid organ cancers.

    Galleri® – Analyzing Cell-Free DNA (cfDNA) for Cancer Detection

    Galleri®, another groundbreaking blood test, detects over 50 types of cancer and predicts the origin of cancer signals with high accuracy. This test examines the methylation patterns of cell-free DNA (cfDNA) found in the bloodstream. Methylation patterns, which regulate gene expression, can be altered in cancer, contributing to tumour growth. By leveraging next-generation sequencing (NGS) and machine-learning algorithms, Galleri® analyses the methylation patterns of cfDNA to identify cancer-specific abnormalities. These patterns provide valuable information about the presence and origin of potential cancers.

    Accuracy & Sensitivity of Each Test

    Trucheck™ demonstrates an overall sensitivity ranging from 82.5% to 88.2% for different cancer types. It boasts a specificity of 99%, correctly identifying 99 out of 100 individuals without cancer. False positives occur at an estimated rate of 1% to 3% according to the studies available so far. Trucheck™ has been designed as a complement to, not replacement for, standard cancer screening, offering peace of mind to individuals with negative results while prompting further tests or referrals for those with positive results.

    Galleri®, as demonstrated in the SYMPLIFY study, achieved a sensitivity of 66.3% overall, ranging from 24.2% for stage I cancers to 95.3% for stage IV cancers. This demonstrates Galleri’s ability to detect cancer signals across various stages but that it is most reliable with later-stage tumours. With a positive predictive value (PPV) of 75.5% and a negative predictive value (NPV) of 97.6%, Galleri®shows promise in accurately identifying individuals with cancer. The test’s specificity stands at 98.4%, further enhancing its precision in distinguishing cancer from non-cancer cases.

    Availability & Cost – Which Test is More Accessible?

    Trucheck™ is available as a standalone test or add-on service for patients undergoing health screening at Coyne Medical and several other private clinics in London and beyond. It may not be covered by healthcare insurance or the NHS prior to a formal cancer diagnosis. Further diagnostic procedures and referrals prompted by positive results may require self-payment.

    On the other hand, Galleri® is currently being evaluated in clinical trials and is not widely available outside of these trials. The SYMPLIFY study demonstrated its potential in a cohort of patients referred for diagnostic investigations related to suspected gynaecological, lung, and gastrointestinal cancers. It is not currently available in the UK in private care. It is only available through NHS research trials. 

    Considerations and Future Implications:

    Both Trucheck™ and Galleri® have the potential to revolutionise cancer screening, but it’s important to consider certain factors. Trucheck™ offers a broader range of tests for different cancer types, while Galleri’s focus lies in detecting over 50 cancer types. Trucheck™ uses CTCs and their clusters as biomarkers, primarily for solid organ malignancies, whereas Galleri® examines cfDNA methylation patterns.

    While Trucheck™ and Galleri® boast impressive sensitivity, it’s crucial to understand that false negatives can still occur. Neither test can replace standard screening methods such as mammograms, colon cancer screening, or cervical screening. Additionally, the emotional impact and potential for anxiety associated with both tests’ results should be taken into consideration.

    Looking ahead, the development of advanced blood tests like Trucheck™ and Galleri® brings us closer to a future where early cancer detection becomes a reality. These tests have the potential to complement existing screening methods, offering individuals a comprehensive and personalised approach to cancer prevention and treatment.

    Trucheck™ and Galleri® blood tests represent groundbreaking advancements in cancer screening, utilising cutting-edge technologies and scientific understanding to improve early detection rates. Trucheck™ focuses on CTCs, while Galleri® examines cfDNA methylation patterns. Both tests demonstrate considerable accuracy and hold promise for transforming cancer diagnosis and treatment.

    It is essential to consult with healthcare professionals to determine the most suitable screening approach based on individual risk factors, age, and personal medical history. By considering these innovative blood tests alongside standard screening methods, we move closer to a future where early cancer detection becomes the norm, leading to better outcomes and improved quality of life. Trucheck™ cancer screening blood test is available at Coyne Medical. Learn more on our website here.

    Book a Cancer Blood Test in London at Coyne Medical

    It is essential to consult with healthcare professionals to determine the most suitable screening approach based on individual risk factors, age, and personal medical history. By considering these innovative blood tests alongside standard screening methods, we move closer to a future where early cancer detection becomes the norm, leading to better outcomes and improved quality of life. Trucheck™ cancer screening blood test is available at Coyne Medical.

    British Association of Sports and Exercise Medicine  ·  European Atherosclerosis Society  · 
    Independent Doctors Federation

    As seen in The Independent, The Daily Mail and Tatler

    For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.