The Subtle Art of Dodging a Biopsy Needle: Insights into Prostate Cancer Screening
Imagine for a moment, a routine test that’s as easy as a light morning jog but as nerve-wracking as a Six Nations Grand Slam decider. That’s the prostate-specific antigen (PSA) test. For many, it’s a simple, non-invasive blood test. Yet, it’s shadowed by the anxiety of what might follow. It’s cheap, it’s easy, but with its low specificity, the real cost might be unnecessary worry and invasive follow-ups.
The Science Behind PSA and its Limitations
PSA testing is a frontline defender in the battle against prostate cancer. Yet, its role has sparked as much debate as it has admiration. Why? Because elevated PSA levels don’t exclusively point to cancer. From benign prostate enlargement to prostate inflammation, several non-cancerous conditions can set that needle twitching. This leads to a cascade of often unnecessary biopsies. The result is overdiagnosed patients living with the label of a cancer that would have remained harmless.
Innovations in Prostate Cancer Screening: The Stockholm3 Study
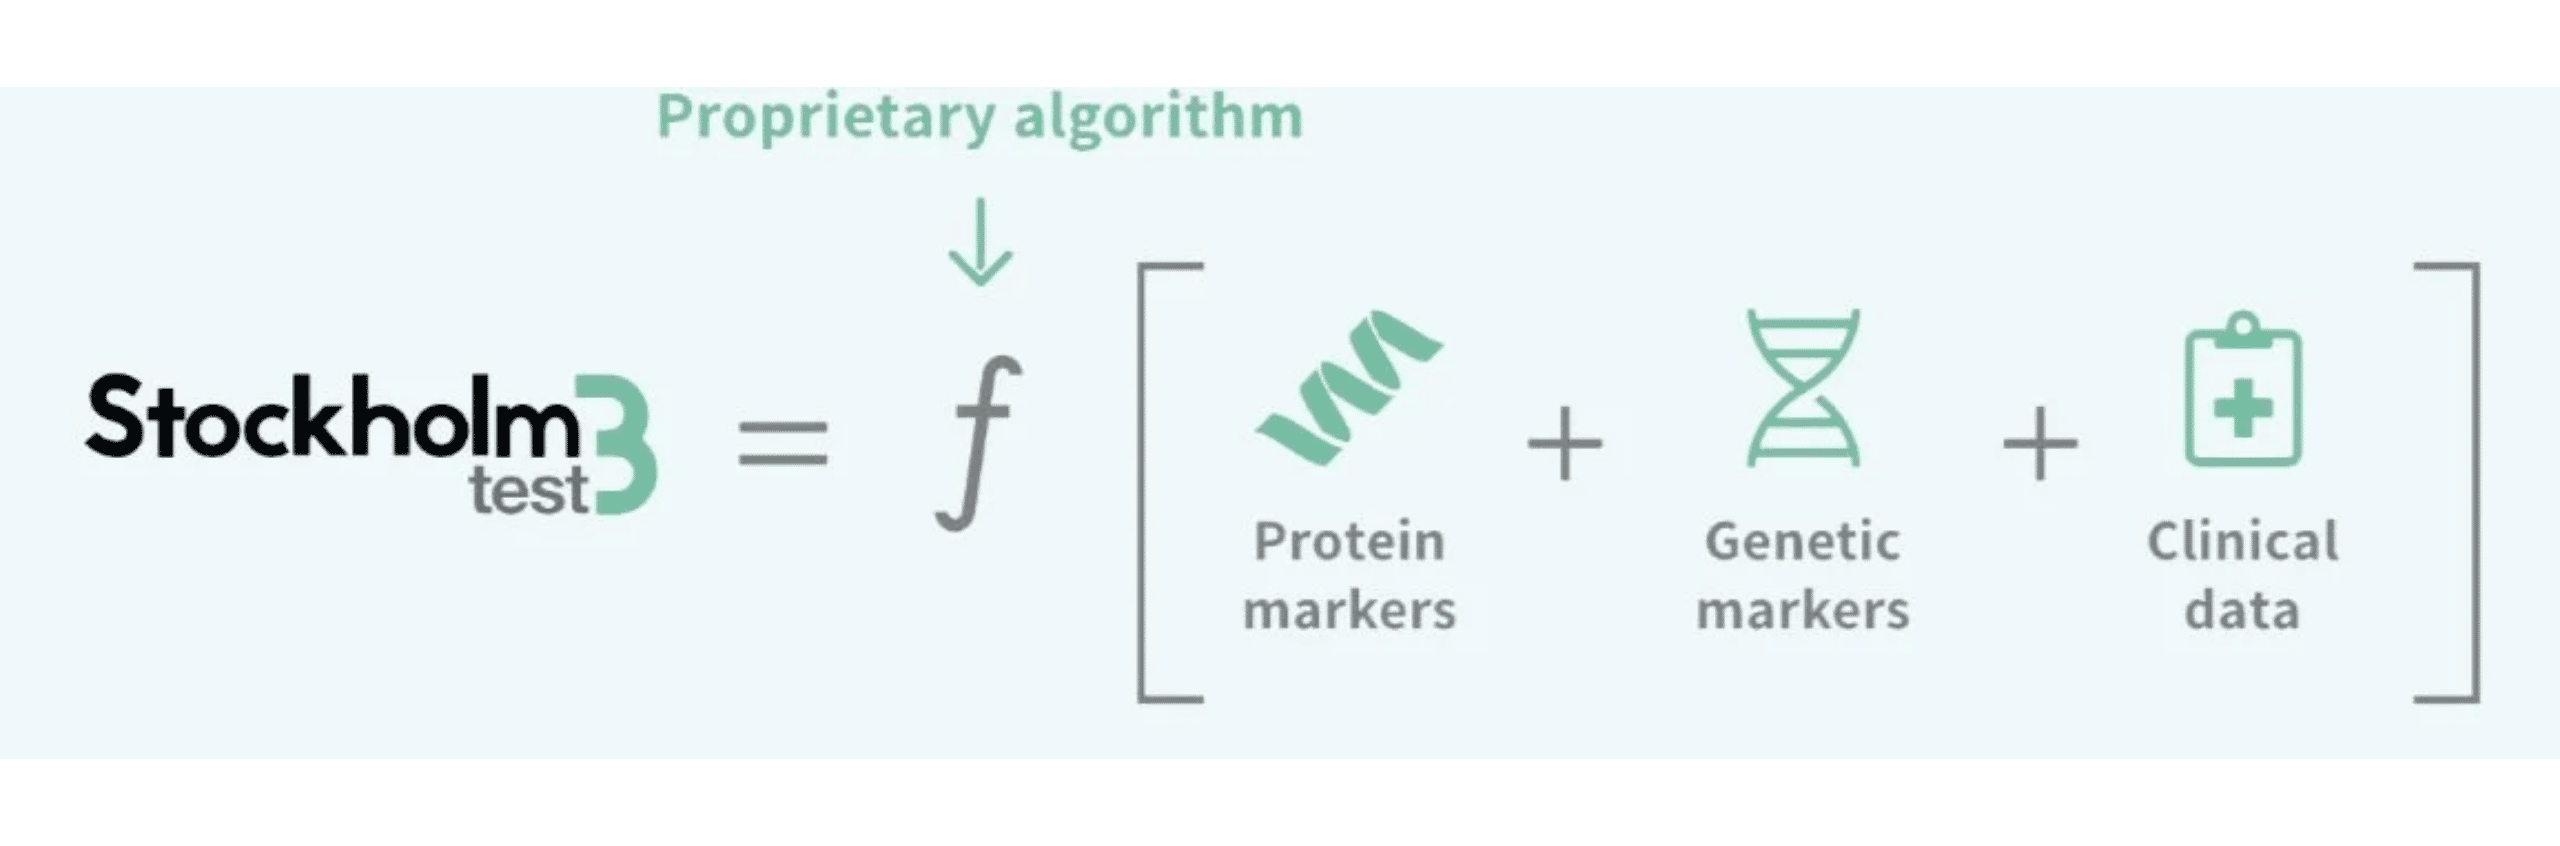
Enter the Stockholm3 (STHLM3) test, a sophisticated algorithm developed by Grönberg et al. The Stockhol3 sounds like the name of an Indie band. However, it could be likened to a finely tuned diagnostic orchestra. The exact opposite of the chaos you might encounter at your child’s assembly. This orchestra, however, is playing a symphony of biomarkers, genetic markers, and clinical data. It is designed to harmonise the detection of significant cancers while reducing the cacophony of unnecessary biopsies. The STHLM3 study showed a reduction in prostate biopsies by 32% compared to PSA testing alone, without missing a beat on detecting high-grade cancers.
Diving Deeper: The Reflex Test and its Importance
The refinement doesn’t stop there. The STHLM3 serves as a reflex test in prostate cancer screening. As such it steps in when PSA levels rise to discern whether that rise truly suggests cancer. This selective approach ensures that only men at higher risk face the biopsy needle. This is a smarter, strategy that not only spares unnecessary pain but also cuts through the cloud of anxiety that hovers over many after a PSA test. The National Institute of Clinical Excellence carried out an innovation briefing on the Stockholm3. The briefing noted “that the technology has the potential to improve diagnostic accuracy leading to a reduction in unnecessary MRI and biopsies.” Prostate Cancer Research has asked that such tests become more widespread.
Global Validation and Ethnic Diversity
The STHLM3’s performed well in Sweden. However, the question remained: How well does it perform on the world stage? The SEPTA trial aimed to answer just that, testing Stockholm3 across a variety of ethnic groups in North America. Sensitivity in medical testing refers to the ability of a test to correctly identify those with the disease (the true positive rate). In contrast, specificity measures a test’s ability to correctly identify those without the disease ( the true negative rate). The trial demonstrated non-inferior sensitivity and a significant boost in specificity. This suggests that Stockholm3 could reduce unnecessary biopsies across ethnically diverse populations without missing those cancers that truly threaten well-being. This is, of course, incredibly useful for us given that we are based in London with it’s immense ethnic diversity.
Looking Forward: The Impact of Stockholm3 on Prostate Cancer Screening
New technologies in medicine are being rapidly developed. We are on the cusp of a new era in medical diagnostics. The Stockholm3 model presents a beacon of hope. It promises a future where the fear of overdiagnosis is significantly diminished. It also offers a journey from prostate cancer screening to diagnosis that respects both the mental and physical sanctity of patients. It’s also a testament to how far we’ve come in understanding and managing prostate cancer.
Conclusion
In an era where medical technology leaps forward by bounds, the evolution of prostate cancer screening from PSA to Stockholm3 is not just about scientific achievement. It’s about managing the delicate balance between vigilance and quality of life. In medicine, we don’t always get that right. For those facing the spectre of prostate cancer, it offers a new narrative, one where the screening process is as thoughtful and refined as the care they deserve.
Contact us at contact@coynemedical.com to book your Stockholm3 test.

DR J HUGH COYNE
MBBS BSc PGDip (with merit) MRCGP DRCOG DCH
Dr Hugh Coyne is a GP and co-founder of Coyne Medical, a private preventive health clinic at 660 Fulham Road, London. He trained at Imperial College London and has been in practice for over twenty years, with a particular focus on cardiovascular risk, metabolic health, and exercise medicine. After qualifying as a GP he went on to train in sport and exercise medicine, bringing a distinctly practical approach to prevention and long-term health.
British Association of Sports and Exercise Medicine · European Atherosclerosis Society ·
Independent Doctors Federation
As seen in The Independent, The Daily Mail and Tatler
For educational purposes. This article is written by a practising GP and is intended to inform, not replace a consultation with your own doctor. It does not constitute medical advice. A note on clinical guidelines: Coyne Medical is an independent private clinic. Our approach is guided by the best available evidence, tailored to each individual. This may go beyond standard NHS or NICE guidance, which is designed for population-level care and weighted by resource constraints.